

AI Analysis of 400,000 Reddit Posts Reveals Underreported Side Effects of GLP-1 Medications
Key Takeaways:
- University of Pennsylvania researchers used artificial intelligence to analyse more than 400,000 Reddit posts from nearly 70,000 users discussing semaglutide and tirzepatide, identifying symptoms that may be underrepresented in clinical trials and official regulatory information.
- Reproductive symptoms, including menstrual irregularities, and changes in body temperature, such as chills and hot flashes, emerged as signals particularly worth investigating, alongside fatigue, which was the second most frequently reported complaint.
- The findings show associations in what people discussed online, not proof that GLP-1 medications cause these symptoms, but the researchers suggest “computational social listening” could become a fast, early detection system for emerging drug safety concerns.
Listening to patients at scale
Artificial intelligence is offering researchers a new way to hear what patients are saying about widely used GLP-1 medications. After analysing more than 400,000 Reddit posts, a team at the University of Pennsylvania identified several symptoms reported by people using semaglutide (Ozempic, Wegovy and Rybelsus) and tirzepatide (Mounjaro and Zepbound) that may not be fully reflected in clinical trials or official regulatory information.
The study, recently published in Nature Health, examined more than five years of posts from nearly 70,000 Reddit users. Two categories of symptoms stood out as particularly deserving of further investigation: reproductive symptoms, including changes to menstrual cycles, and problems relating to body temperature, such as chills and hot flashes.
Importantly, the findings do not establish that the medications caused these symptoms. Rather, the researchers say that this vast collection of spontaneous patient reports may reveal signals that merit closer examination.
“Some of the side effects we found, like nausea, are well known, and that shows that the method is picking up a real signal,” says Sharath Chandra Guntuku, Research Associate Professor in Computer and Information Science (CIS) at Penn Engineering and the study’s senior author. “The underreported symptoms are leads that came from patients themselves, unprompted, and clinicians could potentially pay attention to them.”
What patients report outside clinical trials
Clinical trials are designed to determine whether treatments work and to identify significant safety problems. However, they cannot necessarily capture every symptom that matters to patients once a medication is being used by a much larger and more varied population.
“Clinical trials generally identify the most dangerous side effects of drugs,” adds Lyle Ungar, Professor in CIS and a co-author on the study. “But they can fail to find what symptoms patients are most concerned about; even though social media is not necessarily representative, a large collection of posts may reflect additional concerns.”
This distinction is an important one. The study identified associations in what people discussed online, not evidence that GLP-1 medications were responsible for those experiences.
“We can’t say that GLP-1s are actually causing these symptoms,” notes Neil Sehgal, the study’s first author and a doctoral student in CIS advised by Guntuku and Ungar. “But nearly 4% of the Reddit users in our sample reported menstrual irregularities, which would be even higher in a female-only sample. We think that’s a signal worth investigating.”
Using social media as an early health signal
The idea of mining online conversations for clues about drug safety predates the current AI boom. In 2011, Ungar took part in one of the earliest efforts to use content created by internet users to identify possible adverse effects of medications.
Social media can capture experiences that patients discuss with one another but may never formally report to a doctor, drug manufacturer or regulator.
“Online patient communities work a lot like a neighborhood grapevine,” says Ungar. “People who are living with these medications are swapping notes with each other in real time, sharing experiences that rarely make it into a doctor’s office visit or an official report.”
Since then, online patient communities have grown enormously. This has made social media a potentially valuable source for understanding how medications affect people in everyday life, although gaining access to platform data has become more difficult.
The researchers emphasise that traditional clinical research remains essential, but online conversations can provide information far more quickly when millions of people begin using a medication.
“Clinical trials are the gold standard, but by design, they are slow,” says Guntuku. “This is not a replacement for trials, but it can move much faster, and that speed matters when a drug goes from niche to mainstream almost overnight.”
How AI makes large-scale analysis possible
One of the biggest obstacles to this kind of research has always been scale.
Guntuku describes the approach as “computational social listening”, which uses computational methods to identify patterns across large collections of online conversations about health.
Patients, however, rarely describe their symptoms using standardised medical terminology. One person might describe feeling unusually cold, another might mention constant chills, while a clinician could categorise both experiences using a specific medical term.
Researchers therefore need a way to translate everyday language into standardised categories. One important reference is the Medical Dictionary for Regulatory Activities (MedDRA), which provides terminology widely used to classify medical conditions, symptoms and adverse events.
Previously, matching vast numbers of informal social media posts to standardised medical terminology required an enormous amount of work, limiting how much data researchers could realistically analyse.
Large language models such as GPT and Gemini are changing that, allowing researchers to process and categorise huge volumes of text more quickly and consistently.
“Large language models have made it possible to do this kind of analysis much faster with a level of standardization that could be difficult to achieve before,” says Sehgal.
Unexpected symptoms emerge from 400,000 posts
The researchers stress that Reddit users do not represent the wider population of people taking GLP-1 medications. Reddit users tend to be younger, are more likely to be male and are disproportionately based in the United States.
Despite this limitation, the analysis produced a reassuring sign that the approach was detecting genuine patterns: many of the symptoms discussed by Reddit users closely matched the already known effects of semaglutide and tirzepatide.
Around 44% of users included in the study described at least one side effect. Gastrointestinal problems were the most common, consistent with the nausea and other digestive issues already associated with these medications.
More intriguing were symptoms that appeared frequently enough to attract the researchers’ attention but may not be as well represented in current drug labels or conventional adverse event reports:
- Reproductive symptoms: nearly 4% of users who reported side effects described reproductive symptoms, including changes to menstruation such as bleeding between periods, heavy bleeding and irregular menstrual cycles.
- Body temperature changes: users described chills, feeling unusually cold, hot flashes and symptoms resembling a fever.
- Fatigue: this was the second most frequently reported complaint in the Reddit data, even though relatively few clinical trials reported fatigue often enough for it to meet established reporting thresholds.
For healthcare professionals prescribing or supporting people using these medications, findings like these are a reminder of the value of asking open questions about how patients are feeling, beyond the side effects most commonly discussed. Clinicians wishing to build confidence in this area may find The College of Contemporary Health’s GLP-1RAs in Focus CPD course a useful way to deepen their understanding of these therapies and the conversations that surround them.
Why menstrual and temperature changes are of interest
One possible reason these reports caught the researchers’ attention involves the hypothalamus, a small but vitally important region of the brain. Among its many roles, the hypothalamus helps regulate hunger, hormones, reproduction and body temperature.
“These drugs are thought to work by engaging part of the brain called the hypothalamus, which helps regulate a wide variety of hormones,” says Jena Shaw Tronieri, Senior Research Investigator at Penn’s Center for Weight and Eating Disorders and a co-author of the study. “That doesn’t mean the medications are necessarily causing these symptoms, but it could suggest that reports of menstrual changes and body temperature fluctuations are worth studying more systematically.”
The researchers are not suggesting that this biological link proves GLP-1 medications are responsible. Instead, it provides a further reason to test these patient-reported patterns more rigorously through controlled research.
Turning online conversations into research leads
For now, the team hopes the results will encourage scientists and clinicians to pay closer attention to the symptoms that patients repeatedly discuss online.
“They’re clearly on patients’ minds, and that’s worth paying attention to,” says Sehgal.
The researchers also plan to extend their analysis beyond Reddit and beyond English-language communities. Doing so could help determine whether the same patterns emerge among different groups of people and across different social media platforms.
“We don’t really know yet whether what we’re seeing on Reddit reflects the experience of GLP-1 users globally, or whether it’s particular to the kind of person who posts on Reddit in the United States,” Ungar says.
An early warning system for emerging health concerns
In the longer term, rapid AI analysis of online patient conversations could become an early detection system for emerging health concerns involving medications, supplements and wellness products.
This could be especially valuable for substances that gain popularity online faster than conventional research can keep pace. Loosely regulated or unregulated products, including injectable peptides, can spread rapidly through communities on Reddit, TikTok and other platforms, meaning that discussions among users may offer some of the earliest indications of unexpected effects.
“The whole point of this kind of approach is that it can move quickly, and that’s exactly when it’s most valuable,” says Guntuku.
The study was conducted at the University of Pennsylvania School of Engineering and Applied Science. The authors report no outside funding. Tronieri reports receiving an investigator-initiated grant, on behalf of the University of Pennsylvania, from Novo Nordisk, and receiving consulting fees from Currax Pharmaceuticals, LLC. The other authors report no conflicts of interest.
CCH insight
As more people use GLP-1 medications, healthcare professionals are increasingly hearing about experiences that go beyond the most familiar side effects. Understanding how these therapies work, and how to have informed, supportive conversations with patients about what they are experiencing, is becoming an essential part of practice.
GLP-1RAs in Focus from The College of Contemporary Health is designed to help healthcare professionals strengthen their knowledge of GLP-1 receptor agonists and support patients with confidence.
Explore GLP-1RAs in Focus today →
Source: University of Pennsylvania School of Engineering and Applied Science
Read More
Life After Cancer: New Digital System Aims to Support Young People Living With the Late Effects of Treatment
Key Takeaways:
- The late effects of cancer treatment can emerge months or even years later and may include cardiovascular disease, infertility, chronic fatigue, and psychological, cognitive and socioeconomic difficulties – often at a formative stage of a young person’s life.
- The Horizon Europe-funded LATE-AYA project (2025–2030) is developing an AI-based digital phenotyping system using smartphones and wearable devices to provide personalised follow-up support to young people who have survived cancer.
- People with lived experience of cancer are helping to design the technology from the outset, so that it reduces anxiety rather than adding to it and remains connected to real healthcare.
When treatment ends but the story continues
For a young person, completing cancer treatment can mark a long-awaited return to education, work, relationships and plans for a family. Medically, however, the story does not always end there, as the late effects of cancer treatment may emerge months or even years later.
This challenge was at the centre of the European webinar “Not the End of the Story: Understanding Late Effects of Cancer Treatment in AYA Cancer Survivors,” where researchers, healthcare professionals and patient advocates discussed life after cancer for adolescents and young adults (AYA). The moderator, cardiologist Dr Miha Bogdan of the Medical University of Gdańsk, highlighted that late effects may include not only cardiovascular disease and fertility problems, but also anxiety, depression, cognitive difficulties, and social and occupational challenges.
Professor Asta Pundzienė of Kaunas University of Technology (KTU) presented the international LATE-AYA project, which is exploring how artificial intelligence, smartphones and wearable devices could offer more personalised support to young people after cancer.
Surviving cancer is not the end of the story
Cure rates among children and adolescents can reach around 80 per cent, and as the number of people who have survived cancer grows, so does the question of what happens to their health five, ten or twenty years later. Late effects can include cardiovascular disease, metabolic and endocrine disorders, infertility, chronic fatigue, and psychological and cognitive difficulties – often emerging while young people are studying, starting careers, building relationships or planning a family.
“Alongside cardiovascular, endocrine and fertility problems or chronic fatigue, there can be nutritional, cognitive, psychological and socioeconomic consequences that affect a person’s everyday life. These are no less important than the physiological difficulties that may follow active cancer treatment,” Professor Pundzienė said.
The most difficult period may be between appointments
Paradoxically, one of the hardest stages may begin once active treatment ends. Regular tests and appointments give way to less frequent contact, leaving individuals to judge for themselves whether a new symptom is harmless or a sign of something more serious.
“After active treatment is completed, cancer survivors may feel left alone because their next appointment may be a month away. Every runny nose or pain can be experienced much more intensely by someone who has had cancer than by someone without that experience,” Professor Pundzienė explained.
Care also becomes fragmented, with people moving from a single oncologist to a general practitioner, cardiologist, psychologist and other specialists. Patient advocate and psychologist Katiana Maloli, herself a cancer survivor, described learning only many years after treatment that she needed regular cardiac check-ups because of the potential cardiotoxic effects of her therapy. People in her position, she argued, are often expected to manage their long-term health without enough information to do so confidently.
Can a smartwatch help doctors provide better follow-up care?
Running from 2025 to 2030, LATE-AYA aims to develop an AI-based digital phenotyping system that brings together everyday data from smartphones and wearable devices to understand changes in a person’s physical, psychological and social well-being. The project involves 19 organisations, including KTU and Lithuania’s National Cancer Institute, and is coordinated by the Technical University of Madrid.
“Our first goal is to empower cancer survivors through a personalized digital follow-up environment and to improve their quality of life by helping them manage the late effects of treatment,” said Professor Pundzienė.
The approach combines smart sensing, AI-driven risk prediction, a chatbot, coaching and education, and the platform will be tested using prospective data from smartwatches and smartphones. Crucially, researchers are not starting with the question “What can AI do?” but rather “What do survivors actually need?”
For healthcare professionals keen to understand how tools such as AI-driven risk prediction and chatbots are beginning to shape patient care, The College of Contemporary Health’s AI Essentials for Primary Care course offers a practical grounding in how artificial intelligence is being applied in clinical settings.
Health monitoring should not become another source of anxiety
For someone who has already experienced cancer, constant health alerts could increase anxiety rather than reduce it. LATE-AYA therefore began with focus groups across Europe, asking young people who had survived cancer what support they actually need. The findings revealed a clear need to bridge the information gap between appointments.
“Sometimes a person feels pain and immediately wants to know: could this be related to a recurrence, or is it simply a virus? Having an answer could make them feel more secure and reduce anxiety. We hope the LATE-AYA system will be able to help with these seemingly small but very important questions that arise when survivors are on their own and do not have structured support from the healthcare system,” Professor Pundzienė said.
The aim is not to turn people into constant self-monitors, but to provide reassurance, help them understand when a change matters and guide them towards professional support when needed.
People with lived experience are helping to design the technology
Cardiologist Dr Amelia Stepnowska, presenting the MAYA project, argued that effective digital follow-up should be understandable, actionable and connected to real healthcare, helping to identify when human support is needed rather than replacing clinicians. LATE-AYA follows the same principle, and its development began with living labs and focus groups in which people with lived experience of cancer shaped ideas for the system.
Katiana Maloli went further, arguing that involving patients should not be a “tick-box” exercise. People with lived experience, she said, should be involved from the earliest stages to help determine whether a solution is understandable, practical and genuinely relevant.
Lithuania’s role and the future of survivorship care
LATE-AYA is a Horizon Europe project with a budget of more than €6.2 million. Professor Pundzienė leads KTU’s contribution, while a National Cancer Institute team with experience in wearable device research – including Dr Edita Baltruškevičienė, Assoc. Prof. Dr Audrius Dulskas and Dr Jonas Venius – also takes part, meaning Lithuania is helping to develop and evaluate new digital health approaches, not simply use them.
As more young people survive cancer, success can no longer be measured by survival alone. It also depends on whether people can return to education and work, build relationships, understand their long-term health risks and know where to seek help. Digital medicine may help maintain the connection between patient and doctor between appointments – because cancer treatment may end, but life after cancer continues.
CCH insight
Projects such as LATE-AYA show how quickly AI, wearable technology and digital follow-up are moving from research into real-world care. As these tools develop, healthcare professionals will increasingly be asked to interpret AI-generated insights, recognise their limitations and help people use them safely alongside clinical support.
Build your confidence in this fast-moving area with AI Essentials for Primary Care from The College of Contemporary Health – a CPD course designed to help clinicians understand the role of artificial intelligence in everyday practice.
Explore AI Essentials for Primary Care today →
Source: Kaunas University of Technology (KTU)
Read More
Digital Health Is Redefining Patient Expectations of Care
Key Takeaways:
- Consumers used to personalised digital experiences in banking, retail and entertainment now expect the same convenience and personalisation from healthcare, according to a 2024 Deloitte study.
- Patients are already using digital health services widely: in Spain, 72.48% of survey respondents had used online medical appointments, and older patients and caregivers valued patient portals for their convenience.
- A 2026 OECD report found that patients who have to repeat information that should already be in their health records report worse experiences of trust, quality of care and person-centred care.
The overlooked patient perspective
Professional forums are increasingly focusing on how digital health can contribute to clinical workflows, from automating administrative tasks and analysing imaging studies to segmenting patient groups. However, these discussions often overlook the role of patients themselves, and how digital health is changing their expectations and perceptions of their own healthcare needs.
The growing availability of services that combine effectiveness with patient care and convenience may also be influencing what patients expect from the healthcare system as a whole.
Convenience as a competitive advantage
A 2024 Deloitte study indicated that healthcare systems could gain a competitive advantage by ensuring that their virtual health offerings prioritise convenience and respond to consumer preferences.
According to the report, “today’s consumers, accustomed to highly personalized virtual experiences in banking, retail, and entertainment, now expect the same level of convenience and personalization in their interactions with the healthcare system.”
This shift highlights a key challenge for the healthcare sector: aligning organisational strategies with growing consumer demand for accessible digital health solutions.
For healthcare professionals looking to understand how digital and AI-driven tools are entering everyday practice, The College of Contemporary Health’s AI Essentials for Primary Care short course offers a practical starting point for building confidence in this rapidly evolving area.
Private investment in digital health
Private sector companies are also increasing their investment in digital health.
One example is the recent acquisition of Reimagine Care, a US company that provided virtual care to people with cancer outside the hospital setting, by Cureety, a French healthtech company specialising in the remote monitoring of people with cancer. In 2023, Cureety became the first company in France to receive national reimbursement for the remote monitoring of people with cancer.
Among other features, the company offered a patient interface that supported:
- simple, user-friendly symptom reporting
- secure and ongoing communication with healthcare teams
- reminders
- access to educational content selected and adapted to each person’s treatment and stage of disease
The platform also supported the digitisation and automation of care processes, the monitoring of treatment-specific toxicity, patient classification, the generation of real-world data, and the delivery of specialised educational content to both patients and healthcare professionals at the appropriate point in the care process. Taken together, these functions illustrate how digital health services are evolving.
How patients are using digital health
The question, then, is whether these new approaches to healthcare are changing what patients seek. Several studies have highlighted the value that patients place on online health platforms.
A recent article in the Journal of the American Geriatrics Society examined patient and caregiver expectations regarding the use of patient portals in geriatric care. Users considered patient portals beneficial, particularly because they were convenient and allowed them to avoid in-person care.
In Spain, data from the national survey “Supply and Demand for Users of eHealth Services in Spain”, published in the Journal of Medical Internet Research in 2023, showed that online medical appointments were the most widely used eHealth service. Overall, 72.48% of respondents had used online medical appointments at some point.
The question of trust
While convenience is one consideration, trust is another fundamental issue. Greater access to information that is readily available and easier to understand could strengthen patients’ trust in healthcare professionals and in the healthcare system more broadly.
The 2026 report Building People-Centred Digital Health Systems from the Organisation for Economic Co-operation and Development (OECD) concluded that “When patients have to repeat information that should already be available in their health records, they report significantly worse experience across key patient indicators: trust in the healthcare system, experienced quality of care, and person-centered care.”
However, the report also noted: “Truly patient-centered digital health depends not only on electronic systems but also on patient awareness of access rights, practical tools to retrieve and use data, support for health and digital literacy, and policy frameworks that prioritize patient control over the use of their own health information in line with the OECD Health Data Governance Recommendation.”
Redefining quality care
The debate, therefore, centres on whether healthcare systems need to pursue greater resolution of patients’ needs while also developing a new understanding of what constitutes quality care in a digital age.
This article was translated from El Médico Interactivo on Univadis, part of the Medscape Professional Network.
CCH insight
As patient expectations shift towards convenience, personalisation and seamless access to information, healthcare professionals have a growing role in helping digital tools work well for the people they care for. Our AI Essentials for Primary Care CPD short course helps primary care professionals build a practical understanding of AI and digital innovation in everyday practice.
Explore AI Essentials for Primary Care →
Source: Medscape
Read More
New Virtual Care Programme Aims to Transform Severe Obesity Management in Western Sydney
Key Takeaways:
- Nepean Blue Mountains Local Health District (NBMLHD) is building “Living Well Virtual Care”, a 12–18 month virtual programme offering evidence-based, multidisciplinary care to adults living with severe obesity in Western Sydney.
- The programme is modelled on the internationally recognised Family Metabolic Health Service (FMHS) adult model of care and is designed for people who face barriers attending hospital-based services, including long travel distances, physical disabilities or severe anxiety.
- Funded through NSW Health’s Translational Research Grants Scheme and supported by the Agency for Clinical Innovation, Living Well has been designed to be scalable across NSW, including in regional and rural communities.
A new digital pathway for severe obesity care
Nepean Blue Mountains Local Health District (NBMLHD) is building the “Living Well Virtual Care” programme, a new digitally enabled clinical pathway designed to improve access to evidence-based severe obesity management in Western Sydney.
Living Well will run as a 12–18 month virtual programme. It draws its inspiration from the successful and internationally recognised Nepean Blue Mountains Family Metabolic Health Service (FMHS) adult model of care.
The programme supports adults living with severe obesity through a holistic, evidence-based, multidisciplinary approach. This approach addresses not only a person’s physical and mental health, but also the social factors that influence their long-term wellbeing.
Extending the reach of an established service
A central aim of Living Well is to reach people who may currently be missing out on specialist care.
“Living Well will allow us to extend the reach of the Family Metabolic Health Service to people who are waiting long periods of time to see us, or who may otherwise never engage with us,” explains Dr Kathryn Williams, Clinical Lead of the Family Metabolic Health Service and Principal Investigator of the Living Well program.
The programme is particularly suited to people who face barriers attending hospital-based services. These include people who live long distances from clinics, people with physical disabilities and people who experience severe anxiety.
Responding to growing demand across NSW
Demand for public obesity services continues to grow across NSW. Without timely intervention, a person’s health and quality of life can deteriorate, increasing the risk of chronic disease, disability and future hospitalisations.
Living Well has been developed as an affordable, scalable response to this challenge. By offering earlier, virtual access to coordinated care, the programme aims to support better health optimisation and ease pressure on emergency departments and inpatient services. These are outcomes that the in-person Family Metabolic Health Service model of care is already delivering.
“Severe obesity is a complex, chronic condition and it requires sustained, coordinated care,” continues Kathryn.
“Living Well will put the right support in place earlier, improving health outcomes for patients while also delivering better value for the health system.”
For healthcare professionals, this emphasis on obesity as a complex, chronic condition requiring sustained and coordinated care reflects the kind of evidence-based foundation covered in The College of Contemporary Health’s Obesity Essentials course, which supports clinicians to strengthen their understanding of obesity management in practice.
What the programme offers
The Living Well Virtual Care programme brings together a range of digital and supportive elements, including:
- On-demand educational content
- Live webinars and group interventions
- Practical resources to support participants to engage their GP in medical weight management and the management of obesity-related complications
- Links to trusted external online resources relevant to severe obesity
- Opportunities for peer connection and support
Alongside engaging with the online content, participants receive one-to-one health coaching.
Designed to scale across the state
Living Well has been designed to be scalable across NSW, including in regional and rural communities, and is supported by the Agency for Clinical Innovation.
“This program will demonstrate how digital care can be used as an extension of high-quality clinical services,” says Kathryn.
“For many patients it will mean timely access to care, greater confidence in managing their health, and a more positive experience as they journey through the health system.”
Funding and research significance
The Living Well Virtual Care Program is funded through NSW Health’s Translational Research Grants Scheme. It is one of three NBMLHD high-impact research projects with the potential to be translated into policy and practice and to build research capability within NSW Health.
CCH insight
As services like Living Well show, effective care for people living with severe obesity depends on clinicians who understand obesity as a complex, chronic condition and can support people through sustained, coordinated care. The College of Contemporary Health’s Obesity Essentials course is designed to help healthcare professionals build confidence in evidence-based obesity management.
Source: Nepean Blue Mountains Local Health District
Read More
Adapting the Machine to the Medicine: New Review Shows How to Make Clinical AI Work
Key Takeaways:
- A new review in the Journal of Medical Internet Research analysed 35 recent studies and found that off-the-shelf large language models must be adapted for medical settings before they can be relied upon for diagnosis, triage and treatment planning.
- Performance depends on the clinical task: retraining the model on task-specific data suited narrow jobs such as detecting cancer in medical images, while connecting the model to live, trusted databases worked well for reasoning through complex guidelines. Hybrid systems combining both performed best of all.
- Most of the evidence to date comes from historical medical records rather than live clinical use, so prospective, real-world testing remains essential before widespread hospital adoption.
Why raw capability is not enough
Generative artificial intelligence has arrived in health care with considerable fanfare, but a new review suggests that the decisive factor is not the sheer power of the underlying model. It is what happens after the model is built. A review study published in the Journal of Medical Internet Research by JMIR Publications concludes that adapting existing language models to the clinical environment is the key to ensuring they can safely and effectively support diagnosis, patient triage and treatment planning in real-world settings.
The research team, led by Anshum Patel, MD, and Joseph Y Cheung, MD, MS, analysed 35 recent studies to understand how different customisation methods affect AI performance. Their conclusion was that standard large language models (LLMs) are undoubtedly capable, but capability alone does not translate into clinical reliability. To be trusted in a consulting room or on a ward, a model has to be tailored specifically for the medical environment in which it will be used.
What adaptation actually looks like
The review examined the two broad routes clinicians and developers can take. The first is retraining, in which a general-purpose model is further trained on specific clinical data or guidelines so that it internalises the patterns and standards of a particular task. The second is connection, in which the model is linked directly to trusted medical databases and draws on that source material at the point of use rather than relying solely on what it absorbed during training.
Both approaches produced meaningful gains. When models were connected directly to trusted medical databases or retrained on specific clinical guidelines, accuracy greatly improved, with some systems matching the diagnostic performance of human doctors. That is a striking benchmark, and it underlines the central argument of the review: the adaptation step is not a technical afterthought but the point at which a general tool becomes a clinical one.
The right method depends on the task
The most successful approach was found to depend heavily on the specific medical task at hand, and this is arguably the review’s most practical finding for anyone evaluating these tools.
For narrow, focused tasks such as detecting cancer in medical images, retraining the AI on specific data worked best. Where the job is well defined and the data are consistent, teaching the model directly on that material produces the sharpest results.
For tasks that require reasoning through complex guidelines, linking the AI to live databases was highly effective. Clinical guidance changes, and a model that consults an authoritative, current source is far better placed than one working from a fixed snapshot of its training data.
However, the researchers determined that the best performance came from hybrid systems, which combine both methods to manage complicated workflows such as stroke triage and oncology cases. These are precisely the situations in which speed, protocol adherence and nuanced judgement all matter at once, and where people presenting with time-critical or complex conditions stand to gain the most from well-designed decision support.
“There is no single best way to adapt AI for health care. The right approach depends on the clinical task, and the next step is making sure these systems are safe, reliable, and useful in real-world patient care,” says Anshum Patel.
Implications for clinical teams
For healthcare professionals, the message is not that they need to become engineers. It is that the questions worth asking about any AI tool offered to a service are increasingly practical ones: what was this model adapted for, what source material informs its outputs, how current is that material, and has it been tested on a population and a workflow resembling ours?
That kind of informed scrutiny is becoming part of everyday clinical literacy, and it is one reason structured professional development in this area has grown in demand. The College of Contemporary Health’s AI Essentials for Primary Care short course is designed for exactly this purpose, helping clinicians understand how these systems are built, where their limitations lie, and how to appraise them responsibly within their own practice.
The evidence gap that still needs closing
While these findings are promising, the researchers note that the vast majority of studies on these AI systems are based on past medical records rather than live patient testing. Retrospective analysis can demonstrate that a system performs well against a tidy historical dataset; it cannot show how that system behaves when confronted with incomplete notes, atypical presentations, or the ordinary time pressures of a busy department.
Before these advanced tools are widely adopted in hospitals, additional prospective, real-world testing is needed to guarantee patient safety and ensure the technology works reliably across different clinical environments. Until that evidence accumulates, the sensible position is one of informed optimism – recognising the genuine potential of adapted clinical AI while insisting that it earns its place through testing in the settings where people actually receive care.
CCH insight
Artificial intelligence is moving quickly from conference agendas into everyday clinical workflows, and the professionals best placed to use it well are those who understand both its strengths and its blind spots. AI Essentials for Primary Care is a CPD-accredited short course from The College of Contemporary Health, built for clinicians who want a clear, practical grounding in how AI tools work, how to evaluate them critically, and how to apply them safely in patient-facing practice.
Explore AI Essentials for Primary Care →
Source: Journal of Medical Internet Research
Read More
Cough Data Captured During Sleep Could Flag Flu and COVID-19 Surges a Week Early
Key Takeaways:
- The UK Health Security Agency (UKHSA) and AI sleep technology company Sleep Cycle have published research showing that cough data collected passively by a smartphone sleep app closely reflects levels of respiratory illness reported through NHS 111 in England.
- Rises in night-time coughing were often observed around a week before increases in influenza and COVID-19 activity, offering an early signal that is not shaped by healthcare-seeking behaviour, laboratory turnaround times or reporting delays.
- The cough signal was found to be robust and regionally consistent, supporting a role for privacy-preserved consumer digital health data alongside, rather than instead of, established public health surveillance systems.
A new kind of respiratory signal
A study published by the UK Health Security Agency (UKHSA) and the AI sleep technology company Sleep Cycle has evaluated whether cough data gathered by a sleep app can give early indications of rising respiratory illness in England. The full results are available on medRxiv.
The researchers concluded that passively collected data of this kind can provide a robust and regionally consistent indicator of community respiratory illness, while also providing early signals for influenza and COVID-19 activity. Taken together, the authors argue, the findings support a wider role for digital health data in public health surveillance.
Crucially, the cough data was not gathered by asking anyone to report symptoms. It was generated automatically overnight, from the sound analysis that the app already performs as part of its everyday function.
Why existing surveillance has blind spots
Current respiratory surveillance in England depends heavily on people seeking care through the NHS. That dependence introduces a series of variables that have nothing to do with how much illness is actually circulating in a community.
Levels of public awareness can change how quickly people make contact with a service. The availability of that service matters too, as do demographic and socioeconomic differences between the populations being observed. Two areas with similar levels of illness may therefore generate very different surveillance figures.
Timing is a further constraint. Established systems are also affected by reporting and laboratory processing times, which means the picture available to public health teams is always, to some degree, a picture of the recent past rather than the present moment.
How the sleep app signal is generated
Sleep Cycle is a smartphone app designed to help people understand and improve their sleep through AI-powered sound analysis. The app listens during the night and interprets the sounds it detects, including coughing.
Unlike traditional surveillance, Sleep Cycle’s cough signal is generated automatically during normal sleep using privacy-preserved, passively collected data, and it is updated daily. That combination produces a near real-time view of respiratory illness activity, refreshed without anyone needing to complete a form, book an appointment or wait for a test result.
Because the data is produced as a by-product of ordinary app use, it sidesteps several of the behavioural and administrative filters that sit between illness in a community and the figures that reach public health teams.
A week’s head start on flu and COVID-19
The researchers found that cough data collected through the app closely reflected levels of respiratory illness reported through NHS 111. The two measures moved together, which is the first thing any candidate surveillance signal has to demonstrate.
More significantly, the two measures did not move together at the same moment. Increases in coughing were often observed around one week before increases in influenza and COVID-19 activity. The authors highlight this as evidence that passive digital health data can provide earlier situational awareness alongside established surveillance systems.
A week is a meaningful interval in respiratory season planning. It is time that can be used to prepare staffing, communicate with the public, and anticipate pressure on services rather than respond to it.
The findings suggest that, used alongside established surveillance systems, passive sleep monitoring could provide a fuller picture of respiratory surveillance data, helping public health experts better understand seasonal trends sooner.
What the researchers said
Professor Steven Riley, Chief Data Officer at UKHSA, said:
“These findings suggest that combining established surveillance approaches with novel digital health signals could contribute to an earlier, richer and more resilient understanding of population respiratory health.
No single surveillance system provides a complete picture of respiratory disease activity, but this shows that passive nocturnal cough monitoring can complement other surveillance systems to provide a timely population-level signal of upcoming disease trends, without being affected by healthcare-seeking behaviour, laboratory turnaround times, backfilling and reporting delays.”
Dr Emil Carlsson, Research Scientist and Co-lead Author, said:
“This study demonstrates that passively collected nightly cough data captures meaningful changes in community respiratory illness.
Equally important, it shows that consumer-generated health data can be transformed into epidemiologically meaningful surveillance signals using rigorous scientific methods while maintaining strong privacy protections.”
Dr Mikael Kågebäck, Chief Technology Officer and Acting Chief Executive Officer at Sleep Cycle, said:
“This study validates a completely new category of health data.
For the first time, we’ve demonstrated that passively generated smartphone data can produce robust population-level health intelligence at national scale, while also providing earlier signals for influenza and COVID-19 activity.
That creates opportunities to strengthen public health surveillance and enable researchers, healthcare organisations and industry partners to build new services for situational awareness and operational decision support.”
Complement, not replacement
Both organisations frame the work in the same way. The cough signal is not presented as a substitute for laboratory confirmation, clinical reporting or NHS 111 data. It is presented as an additional layer that behaves differently from the others, and whose value lies precisely in that difference.
As Professor Riley notes above, no single surveillance system provides a complete picture. A signal that is unaffected by whether people choose to seek care, and unaffected by how long a laboratory takes to process a sample, fails in different ways from the systems already in place. Combining sources with different weaknesses is a well-established way of building a more resilient overall view.
What it means for clinicians and health organisations
For practitioners, the study is a practical illustration of a broader shift. Data generated by consumer devices is increasingly being assessed against the standards applied to conventional health data, and in this case it held up well enough to warrant serious attention from a national public health body.
That shift raises questions clinicians and managers are likely to encounter more often: how such signals are validated, what privacy protections are in place, how to judge the reliability of a consumer-generated dataset, and where these tools genuinely add value to decision-making. Professionals looking to build confidence in this area may find structured CPD useful, and The College of Contemporary Health’s short course AI Essentials for Primary Care is designed to help healthcare professionals understand how AI-driven tools are being applied in practice and how to appraise them critically.
A note on the status of this research
This was reported in medRxiv, The Preprint Server for Health Sciences. The following caution applies, as it does to all preprints:
Preprints are preliminary reports of work that have not been certified by peer review. They should not be relied on to guide clinical practice or health-related behavior and should not be reported in news media as established information.
The findings described here should therefore be read as promising and carefully conducted early-stage research rather than as settled evidence. Peer review may yet refine the conclusions, the size of the reported lead time, or the conditions under which the signal performs best.
CCH insight
Digital health signals are moving quickly from novelty to everyday practice, and healthcare professionals are increasingly expected to interpret them with the same rigour they apply to any other source of clinical or population data.
AI Essentials for Primary Care is a CPD short course from The College of Contemporary Health, developed for healthcare professionals who want a clear, practical grounding in how artificial intelligence is being used across healthcare settings and how to evaluate it responsibly.
Explore AI Essentials for Primary Care →
Source: GOV.UK
Read More
From Years of Uncertainty to Answers: How AI Is Shortening the Rare Disease Diagnostic Odyssey
Key Takeaways:
- ThinkRare, an algorithm at the Children’s Hospital of Eastern Ontario, scans health records to flag children who may need a rare disease referral. It has led to 21 new diagnoses and a 70% success rate so far.
- At Boston Children’s Hospital, a reasoning model built by OpenAI solved all 20 known test cases and contributed to 18 diagnoses among 376 previously unresolved ones.
- Neither tool works alone. Data bias, hallucinations, and clinicians’ tendency to defer to AI mean a human in the loop remains essential.
Why a rare disease diagnosis can take half a decade
For people living with a rare disease, the route to a diagnosis can be long, circuitous, and occasionally never completed at all. Reaching an answer often demands specialist training and technical resources that many clinics simply do not have. In a News and Perspectives article for JMIR, correspondent Simon Spichak reports on how AI initiatives at one children’s hospital in the United States and another in Canada are working to close that gap, and how they could fundamentally reshape the diagnostic experience for children and families living with rare conditions.
For some people, the benefits are already tangible. AI algorithms have helped their doctors reach a diagnosis, and that diagnosis has in turn opened the door to accessibility accommodations, treatments, clinical trials, and further research into their condition. If these tools can be scaled, they could meaningfully shorten what is often described as the diagnostic odyssey – the almost five years, on average, of appointments, medical visits, and frustration that it typically takes to diagnose a rare disease.
Finding the children who are lost in the system
CHEO is helping to lead the way with ThinkRare, an algorithm that scans electronic health records and flags children who may need a referral to a rare disease specialist for further testing.
“The purpose of ThinkRare is to find the patients that aren’t coming to us, that are bouncing around, that are lost in the system,” says Ivan Terekhov, BCom, director of research informatics, AI, and technology at CHEO Research Institute.
The approach targets the very beginning of the diagnostic journey, where children are cycling through appointments without anyone joining the dots. ThinkRare has already prompted genetic sequencing and follow-up in a handful of children, leading to 21 new rare disease diagnoses and a 70% success rate to date. The researchers behind the algorithm are now working on rolling the model out to other hospitals.
Tackling the cases that leave clinicians stuck
BCH is addressing the opposite end of the odyssey, using a reasoning model built by OpenAI to help resolve cases that have defeated clinicians.
Catherine Brownstein, PhD, scientific director of the genetic investigations arm of the Manton Center for Orphan Disease Research at BCH, says she was sceptical at first. When the team fed the reasoning model rare disease cases for which the diagnosis was already known, it initially appeared to falter. Eventually it diagnosed 19 out of 20 cases correctly, and ultimately all 20.
“When we looked at the one that it got wrong,” she says, “we were wrong.” The AI had flagged a second diagnosis that clinicians had missed.
At that point, Brownstein and her team judged the model ready for the real test: helping to solve cases that remained undiagnosed. It proved remarkably successful, with its output leading to 18 diagnoses among 376 previously unresolved cases.
What does AI do that clinicians cannot?
According to a recent report, insufficient physician training may help to explain why people with rare diseases go undiagnosed for so long. ThinkRare addresses this gap by incorporating expert-curated criteria to flag rare diseases that the average doctor might miss, so that those children can be considered for genetic testing.
Even after sequencing, rare disease specialists can take a long time to arrive at a diagnosis, and complicated cases sometimes remain unsolved. Specialists have only a limited amount of time to spend with each family, and may be carrying many cases they are simply unable to revisit.
During her PhD, Brownstein spent six years working on a single family. “There’s just simply not enough geneticists in this world or scientists in this world to do the thorough, in-depth investigations that are necessary to make all the insights possible,” she says.
The reasoning model used at BCH, designed to reason carefully and show its work, was developed using o3 Deep Research, a publicly accessible model. When it identifies a potential genetic mutation that might be causing a child’s symptoms, it presents its chain of reasoning alongside the suggestion. Geneticists then take over, running the tests needed to confirm or rule out the diagnosis.
“But instead of having to go to the sequence and find that variant yourself, it’s presented to you in a way that’s much, much quicker,” says Brownstein.
The insights the model produces may also lead to discoveries that clinicians would not otherwise make. In one instance it surfaced a new genetic variant that might be implicated in vitiligo, an autoimmune condition in which the body attacks the pigment-producing cells in the skin.
“I was speechless,” Brownstein recalls. Her team now has research under way to investigate whether the mutation is causative. If that work bears out, she hopes it could point towards a new treatment.
As tools like these move closer to everyday practice, the demand for clinicians who understand both their promise and their failure modes is rising. Short, focused CPD training such as the College of Contemporary Health’s AI Essentials for Primary Care course is designed for exactly that: helping practitioners get to grips with how these systems work, where they add value, and where human judgement has to stay firmly in charge.
Why there needs to be a human in the loop
Neither model removes the clinician from the process.
ThinkRare’s algorithm is passive, flagging a small number of cases out of several hundred thousand children attending its clinics. Those children still need testing and assessment by a specialist, because the algorithm does not actually predict which condition a child may have.
And because the algorithm is built on clinical expertise and trained on electronic medical records, bias is baked in. “I think we’d be naive to say that there’s not data quality issues or there’s worse data quality for those who are not White and those who do come from rural locations,” notes Alexandre White-Brown, MSc, a genetic counsellor and project manager of ThinkRare. Canada’s diversity is nonetheless well represented within the algorithm’s training dataset, which helps to offset some of these potential issues.
While Brownstein says the reasoning model used at BCH improved rapidly, errors and hallucinations are common with any large language model (LLM). OpenAI’s reasoning model still needs to be used in collaboration with a clinician rather than as a stand-alone tool.
The risk of trusting the machine too readily
Research into human-AI interaction has repeatedly shown that experts may defer to the judgement of an AI system, even when it is wrong.
“Previous studies show that learning from evidence is especially difficult when the evidence is poorer and uncertainty is higher, as in the case of patients with rare diseases,” says Aranzazu Viñas, PhD, an assistant professor at the University of the Basque Country. “Therefore, AI’s errors might be still more difficult to detect in the case of rare diseases.”
Her recent study suggests that doctors will trust an AI’s judgement even when they receive new clinical information showing it to be wrong. Viñas emphasises the importance of conducting “ecological research” to establish whether these errors also appear in real-world settings. Beyond that, she says it is “important to develop strategies and protocols that increase human critical thinking and detection of AI errors.”
The future of AI for rare diseases
BCH is now looking towards further study and model validation, measuring time and cost savings, clinician effort, false positives, and whether using the model actually changes the care people receive. The team is working with OpenAI to democratise access for other researchers and clinicians.
At CHEO, ThinkRare is currently able to spot the low-hanging fruit, but Terekhov points to the data silos created by information locked away in unstructured reports and doctors’ notes. The next iteration of ThinkRare will incorporate LLMs that can access and interpret this material, allowing the system to flag more cases. Scaling the model countrywide will require regulators to sign it off.
What a diagnosis changes for a family
White-Brown explains the impact ThinkRare is already having. Antony was diagnosed with an ultrarare condition called Chung-Jansen Syndrome at 10 years old, after being flagged by the algorithm. The diagnosis provided an explanation for his symptoms, and testing revealed that the same condition affected his brothers and his mother.
“The biggest thing for this family was actually being able to access resources in school that were previously unattainable,” says White-Brown.
CCH insight
AI-assisted triage, diagnostic support, and documentation tools are arriving in clinical settings faster than most training has kept pace with. The College of Contemporary Health’s AI Essentials for Primary Care CPD short course gives healthcare professionals a practical grounding in how these technologies work, how to appraise their output critically, and how to use them safely alongside clinical judgement.
Explore AI Essentials for Primary Care →
Source: JMIR Publications
Read More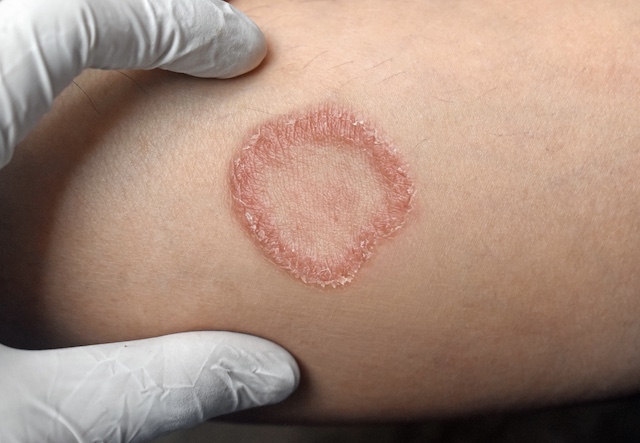
Fungal Disease Is Rising and Underdiagnosed – Can AI Help Close the Gap?
Key Takeaways:
- Fungal diseases affect more than 300 million people each year and are linked to over 3.75 million deaths annually, yet they remain historically underrecognised, difficult to diagnose and poorly tracked compared with viral and bacterial infections.
- A World Health Organization (WHO) blueprint released in June 2026 sets out a framework for countries to raise awareness, build laboratory and surveillance networks, stimulate research and improve access to diagnosis and treatment.
- Australian researchers are finalising an automated surveillance platform that uses AI to extract evidence of fungal disease from electronic medical records, with the biggest obstacle being the standardisation of clinical annotations rather than the technology itself.
A threat that has grown in the shadows
Fungal disease and antifungal resistance are growing global threats that have long sat at the margins of public health planning. They are difficult to detect, difficult to track and, until recently, have attracted comparatively little policy attention. That is beginning to shift, driven by two parallel developments: a new international policy framework and a set of digital health initiatives designed to make fungal infection visible in routine clinical data.
The scale of the problem is substantial. More than 300 million people are affected by fungal diseases every year, and over 3.75 million people die annually. Among patients who are immunocompromised, invasive fungal infections are the “leading cause of mortality and morbidity”, according to a 2025 WHO report.
In recent years, the number of new infections, and especially antifungal-resistant infections, has doubled. Two environmental drivers are implicated. As the climate warms, fungi are adapting to survive at higher temperatures, narrowing the thermal barrier that has historically protected humans from many environmental fungi. Increased flooding events have also contributed to mould growth, which in turn leads to disease spread. A third driver sits outside the clinical environment altogether: the use of fungicides on agricultural crops is a major cause of antifungal resistance encountered in healthcare settings, because agricultural compounds and clinical antifungals share overlapping mechanisms of action.
Despite rising prevalence, fungal infections are still not as common as viral infections, so far fewer diagnostic tools have been developed to test for them. With relatively fewer resources allocated to fungal disease research, surveillance and response, fungal diseases also lag behind bacterial infections in terms of treatment options. Recent policy developments and digital health initiatives are working to change this.
Why fungal diseases are difficult to diagnose and treat
One of the biggest challenges to fungal disease preparedness is underdiagnosis, which makes research, surveillance and response considerably more difficult. Without a diagnosis, there is no case to count, and without counted cases there is no evidence base to justify investment.
“If we don’t have good diagnostic tests, these diseases don’t exist because we don’t know who has them,” said Tom Chiller, MD, former chief of the Mycotic Diseases Branch at the Centers for Disease Control and Prevention.
Chiller adds that diagnosing fungal disease is inherently difficult because fungal cells look similar to human cells, making it challenging to develop a diagnostic test sensitive enough to tell the difference. Fungi are also everywhere around us, in their billions. Exposure is “near universal”, and it is hard to distinguish the colonies that are causing disease from those that are entirely harmless. A positive result, in other words, does not automatically indicate infection.
That same cellular similarity creates a second problem at the point of treatment. Because fungal cells so closely resemble human cells, it remains very challenging to kill one type of cell without also damaging the other, which makes treatment toxicity a major issue for the patients who most need therapy.
There is also the matter of range. Only three major classes of antifungal drugs are available – azoles, echinocandins and polyenes – so resistance carries disproportionate consequences. When a fungal pathogen becomes resistant, there are simply fewer tools left in the toolbox.
New antifungal agents in development
Encouragingly, several new antifungal drugs are at various stages of development and investigation, and may help to address resistance. Oteseconazole and rezafungin have received US Food and Drug Administration approval in recent years, building on the existing antifungal classes and expanding the available arsenal. Two newer treatments, olorofim and fosmanogepix, represent entirely new classes and will hopefully be approved in the coming years. New classes matter more than new agents within existing classes, because they offer options where cross-resistance is less likely.
A blueprint for improving antifungal care
While millions of fungi exist, only a few hundred can cause disease in humans. Some of the most common and well-known fungal diseases include ringworm, vaginal yeast infections, athlete’s foot, skin infections such as sporotrichosis, and mould infections such as aspergillosis, as well as invasive infections including cryptococcal meningitis and candidiasis.
The most dangerous fungal disease is multidrug-resistant Candida auris, which was first identified in a Japanese hospital in 2009 and has been found fatal in 29% to 62% of cases.
Without surveying when these conditions are diagnosed and treated, there can be no accurate picture of which diseases are most prevalent, or of when they become resistant to available antifungal treatments. Stewardship programmes designed to protect against resistance also remain weak and limited in scope, particularly in underresourced countries.
Recognising this gap, the WHO released a new blueprint in June 2026 to help countries begin to create uniform tools to respond to the growing public health threat of fungal disease and antifungal resistance. The report provides a framework with recommendations to guide implementation across four areas: increasing awareness and strengthening public health initiatives; building laboratory networks and surveillance systems; stimulating research and improving access to diagnosis and treatment; and addressing the factors that contribute to disease and resistance.
It also aims to support countries in their disease response and to make more fungal diseases reportable to public health officials. Across the United States, for example, reporting priorities vary between states, and the only fungal diseases prioritised as legally reportable nationally are coccidioidomycosis (Valley fever) and Candida auris – a small fraction of those that can affect human health.
Chiller said he hopes the report will draw more attention to both the prevalence and the morbidity of these infections in order to improve available funding. Increased resources would be particularly useful for investing in new treatments to stave off antifungal resistance.
A digital platform for fungal disease and antifungal resistance surveillance
Alongside the policy work, Australian researchers are in the final stages of launching an automated fungal infection surveillance platform that will digitally survey fungal disease across the continent.
The digital platform, called the Design Thinking Framework, was built from a review of multiple sources of clinical information across a wide array of healthcare settings in Melbourne. It extracts information from electronic medical records (EMRs) using AI trained to detect episodes of fungal disease even when the diagnosis is not explicitly recorded. The tool will also provide a web-based platform accessible to physicians so that they can properly report future episodes of fungal disease and resistance.
Vlada Rozova, PhD, a senior lecturer in AI in Health at Monash University, who originally led the project at the University of Melbourne, said the Design Thinking Framework will be helpful in monitoring what is being prescribed for fungal diseases across a range of hospitals, in order to understand when prescribing leads to resistance and what can be done to reduce it, while also identifying which treatments are most effective for patients.
“It will help clinicians to better evaluate the therapies that they’re providing their patients to know what’s necessary and in what particular types of patients certain antifungal agents are most effective,” said Rozova.
Why the hardest problem is human, not technical
The biggest challenge for Rozova and her colleagues has not been the algorithm. It has been standardising clinical annotations to ensure that reports are consistent across the platform. Getting clinicians to agree on which notes within EMRs indicate fungal disease, and which indicate resistance, has been and will continue to be a complex task, because humans, unlike machines, are not standardised.
“If we can’t get humans to agree on what a fungal disease is, we can’t train a machine to look for it,” said Rozova.
This is a familiar theme across clinical AI. Tools that read free-text records depend on consistent human documentation and shared definitions, which is why clinicians increasingly need a working understanding of how these systems are built, what they can reasonably infer and where they are likely to fail. Practitioners looking to develop that grounding often begin with structured CPD, such as the College of Contemporary Health’s AI Essentials for Primary Care short course, which introduces how AI-driven tools are being applied in clinical practice and how to appraise them critically.
Looking ahead
Increased awareness will hopefully bring increased agreement. With guidance from global bodies such as the WHO, and with new digital surveillance platforms of the kind being finalised in Australia, the global response to fungal infections and antifungal resistance stands to be meaningfully strengthened – provided the diagnostic, documentation and funding gaps are addressed in parallel.
CCH insight
Digital surveillance tools are only as reliable as the clinical documentation that feeds them, and clinicians are increasingly being asked to work alongside AI systems rather than simply receive their outputs. Our CPD-accredited short course AI Essentials for Primary Care is designed for healthcare professionals who want a practical, jargon-free grounding in how these technologies work and how to evaluate them in day-to-day practice.
Explore AI Essentials for Primary Care →
Source: JMIR Publications
Read More
Digital Tools Can Support Young People’s Mental Well-Being – but Human Contact Still Matters
Key Takeaways:
- A York University-led review of 57 studies and more than 40,000 participants finds digital tools can improve young people’s emotional, behavioural, social and cognitive well-being.
- Hybrid models, pairing digital delivery with in-person contact, were the most consistently effective, with benefits sustained at follow-up.
- The evidence base has serious gaps: children from marginalised communities and those aged 0 to 4 are strikingly underrepresented.
Why this review matters
Children and young people are growing up with rising mental health challenges in an increasingly digital world, and those from marginalised communities carry a disproportionate share of that burden. Digital mental health tools have been promoted for years as a way to close the gap, on the assumption that anything delivered through a screen can reach further, faster and more cheaply than traditional services. Until now, the evidence for universal digital and hybrid interventions had never been pulled together and appraised as a whole.
A new landmark systematic review and meta-analysis led by researchers at York University changes that. Examining the effectiveness of universal digital mental health interventions, the study finds that digital tools can positively influence young people’s emotional, behavioural, social and cognitive well-being. The study is currently available online.
What the review examined
The review synthesised 57 peer-reviewed research articles and included data from more than 40,000 participants worldwide. Rather than focusing on interventions aimed at children and young people already identified as needing clinical support, it looked specifically at universal interventions, that is, those offered to whole populations regardless of individual risk. That distinction matters for anyone planning services at scale, because universal provision is where digital delivery is most often proposed as a solution.
The research was led by York University Faculty of Health Professor Rebecca Pillai Riddell, a nationally recognised expert in clinical psychology, alongside York postdoctoral fellow Kaitlin Di Pierdomenico.
“This study is the first of its kind to synthesize universal digital and hybrid interventions for child and youth mental health,” says Pillai Riddell. “It’s clear that digital tools must be embraced but only if we implement them thoughtfully, equitably, and with real-world contexts in mind. We need to invest in research that includes the children most often left behind.”
Hybrid delivery outperformed fully digital approaches
The clearest signal in the analysis was that hybrid models, those that combine digital delivery with some in-person engagement, emerged as the most consistently effective approach. Moderate-certainty evidence supported sustained benefits across multiple psychological domains at follow-up, meaning the gains did not simply disappear once the intervention ended.
This finding pushes back against the assumption that a fully virtual programme is a straightforward substitute for one delivered face to face. The technology appears to work best when it is wrapped around human contact rather than used to replace it.
“This work looked at whether digital mental health tools help, under what conditions, and whose data we actually have,” says Di Pierdomenico. “Hybrid approaches, pairing digital tools with in-person structure, held up better over time than fully virtual ones. We also found real gaps, including underreporting of participant demographics and limited inclusion of younger children and marginalized populations, that matter so universal tools are developed to actually reach all children and youth.”
Benefits across four psychological domains
The analysis revealed significant improvements across emotional, behavioural, social and cognitive psychological domains. Effects were most consistent and most sustainable when digital tools were embedded in supportive, structured settings such as schools.
The implication for commissioners and practitioners is that the delivery context is not incidental to the outcome. A well-designed app or online programme placed into an environment with adults who can prompt, reinforce and follow up appears to perform differently from the same tool handed to a young person to use alone.
That emphasis on structured human contact places renewed weight on the interpersonal skills practitioners bring to digitally supported care. It is the ground covered by CCH’s Behaviour Change Skills – Complete Package, a set of three online CPD short courses in person-centred communication, enhancing motivation and applying CBT in practice, worth six CPD hours in total.
Significant gaps in who the evidence represents
Alongside the positive findings, the study highlights a striking underrepresentation of research involving marginalised populations and younger children aged 0 to 4. This raises concerns about equity and inclusion in the current evidence base.
Two problems compound each other here. The first is straightforward absence: if the youngest children and those from marginalised communities are rarely included in trials, there is no reliable basis for claiming that universal tools work for them. The second is underreporting of participant demographics, which makes it difficult even to establish who has and has not been studied. Universal interventions are, by definition, meant to reach everyone, so evidence drawn from a narrow and poorly described sample is a weak foundation for population-wide rollout.
A national partnership behind the research
The York researchers worked with Strong Minds Strong Kids, Psychology Canada (SMSKPC) for the study, a national charity that promotes children’s mental well-being through psychological science.
“Our history has always been about promoting mental health. This research reinforces the urgency to get promotion right – and get it to the children who need it most,” says Anne Lovegrove, President and Executive Director of SMSKPC and a co-author on the study. “We undertook this study not only to inform our own work but to guide the entire sector toward what actually works in a rapidly changing digital landscape.”
The project was also generously supported by philanthropy from the Jackman Foundation, a longtime champion of youth mental health and of SMSKPC and York University.
What this means for practice
For practitioners and service planners, the review offers a more nuanced brief than either uncritical enthusiasm or blanket scepticism about digital mental health. Digital tools have a demonstrable place in supporting young people’s well-being. They appear to work best when paired with in-person structure, embedded in settings that already provide routine and relationships, and supported by adults who can hold the human side of the intervention.
Equally, the gaps identified in the evidence are a caution against assuming that a tool shown to help one group will help another. Extending reach is only meaningful if the children and young people who are currently least well served are actually included, both in the interventions themselves and in the research that evaluates them.
The full study, Universal Digital Mental Health Interventions for Children and Youth: A Systematic Review and Meta-Analysis, is available open access via npj Digital Medicine.
CCH insight
The strongest finding in this review is that digital tools worked best when paired with human contact and structure. That places the quality of practitioner conversations at the centre of digitally supported care.
CCH’s Behaviour Change Skills – Complete Package brings together three online CPD short courses – Person-Centred Communication, Enhancing Motivation, and Applying CBT in Practice – for six CPD UK hours. It is 100% online, self-paced, and accredited by The CPD Certification Service.
Explore Behaviour Change Skills – Complete Package
Read More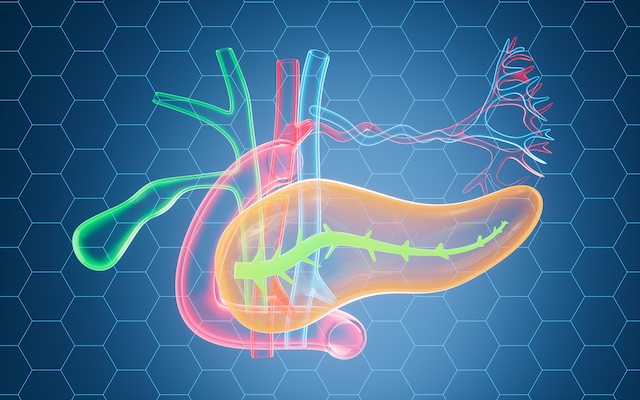
AI Model Detects Diabetes and Sorts Records Into Four Diagnostic Categories
Key Takeaways:
- Researchers have built a machine learning framework that first detects diabetes and then assigns positive records to one of four categories: prediabetes, type 1 diabetes, type 2 diabetes, or diabetes arising from pancreatic disease.
- XGBoost was the authors’ preferred classifier, though the paper reports inconsistent performance rankings across its own tables, with random forest outperforming it in one comparison.
- The framework is a proof-of-concept only. It has not been externally validated, its two stages were trained on separate datasets, and it is not ready for clinical use.
Why diabetes subtyping is a difficult problem
Diabetes is among the most common metabolic conditions worldwide, and its prevalence continues to rise. People living with diabetes typically experience raised blood glucose levels caused by insufficient insulin secretion, insulin resistance, or a combination of the two. Where hyperglycaemia persists, it can lead to serious complications affecting the eyes, heart, kidneys and nerves.
That burden has prompted interest in new strategies for detecting and classifying diabetes using clinical data that is already routinely available. If such tools were externally validated, they could in principle help clinicians identify individuals who warrant further diagnostic assessment, and support decisions about dietary, lifestyle or pharmacological management.
A study accepted for publication in Scientific Reports sets out one such approach: a machine learning (ML) model built on common clinical variables and a derived pancreatic-health index, designed both to detect diabetes and to classify it. The authors are explicit that clinical utility, patient outcomes and quality of life were not assessed.
About the study
The researchers presented an integrated, ML-based approach with two stages. Binary classification was used to determine diabetes status, and multiclass classification was then used to assign records to one of four dataset classes: prediabetes (PD), type 1 diabetes (T1D), type 2 diabetes (T2D), and diabetes from pancreatic disease, also known as pancreatogenic or type 3c diabetes (T3cD).
Two publicly available datasets were used. For the binary task, the team drew on the Pima Indians Diabetes Database, maintained by the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), to separate records into diabetic and non-diabetic. For the multiclass task, they used a dataset from the Kaggle repository. The curated multiclass dataset comprised 21,539 samples, split 60% for training and 40% for testing.
How the models were built and tested
Inputs to the multiclass model included age, body mass index (BMI), waist circumference, cholesterol levels, blood glucose levels, insulin levels, and a derived pancreatic-health index.
Several ML algorithms were compared to identify the most effective approach for each classification task: logistic regression, decision trees, random forests, K-nearest neighbours (KNN), naive Bayes, and XGBoost.
To correct class imbalances, the team applied the Synthetic Minority Oversampling Technique (SMOTE) to the training data only. Hyperparameter tuning was then carried out to identify the best-performing parameter combinations, and the models were retrained using those selected parameters. Finally, the researchers ran a Local Interpretable Model-agnostic Explanations (LIME) analysis on their preferred classifier to examine how individual features contributed to model predictions.
What the models achieved
The authors selected XGBoost as their preferred classifier, although the paper’s reported performance rankings are not consistent across tables. Table 2 gives a value of 0.97 for every evaluation parameter, covering accuracy, precision, recall and F1 score. Table 7, however, reports an accuracy of 95.67% for XGBoost against 96.67% for random forest, with random forest also achieving a marginally higher macro-average ROC-AUC, a measure of how well a model discriminates across the four classes.
The researchers attributed XGBoost’s performance to its capacity to capture complex, non-linear associations between features. In the reported test results, XGBoost correctly classified all prediabetes and T1D records, though some confusion persisted between the T2D and T3cD groups. KNN was the least accurate of the algorithms tested.
This kind of discrepancy between a paper’s headline claim and its own supporting tables is exactly the sort of detail clinicians are increasingly expected to spot for themselves. CCH’s CPD-accredited short course AI Essentials for Primary Care covers structured appraisal of AI tools, including the SAFER Evaluation Framework and how to judge AI output against NHS standards.
Which features drove the predictions
General feature-importance analysis pointed to blood glucose levels, insulin and BMI as the most influential variables. The LIME analysis told a slightly different story, indicating that glucose dominated the model’s predictions, with age and cholesterol making secondary contributions in some classes. BMI, waist circumference, insulin and pancreatic health had comparatively lower influence in the LIME results.
Blood glucose levels showed the strongest reported correlation with the class label, at a Pearson’s correlation of 0.86, while insulin showed a correlation of 0.59. These correlations should be treated with caution, since numerical values were assigned to what are, in fact, nominal disease classes.
Age, BMI and waist circumference showed moderate to strong intercorrelations, ranging from 0.63 to 0.68. Their respective correlations with the target were 0.41, 0.46 and 0.56. Pancreatic health showed a negligible negative correlation of -0.06.
In practice, the model primarily learned blood glucose-based decision patterns, which are consistent with the clinical diagnosis of diabetes. The authors interpreted these patterns as broadly concordant with diabetes pathophysiology and existing clinical knowledge, though that interpretation was not independently validated in clinical practice. On the evidence presented, the model is not ready for clinical use and would require considerably more evaluation before it could support, rather than replace, clinical judgement.
Conclusions and future directions
The study demonstrates an ML framework capable of classifying diabetes status and assigning positive cases to four labels: prediabetes, T1D, T2D and T3cD. The authors suggest the framework could eventually assist with diabetes screening and help guide further diagnostic investigation. Crucially, the study did not establish whether using the model improves care, treatment outcomes, quality of life, or the wider global burden of diabetes.
The varying influence of lipid, pancreatic and body measurements may reflect genuine subtype-related biological differences. Equally, it may be an artefact of dataset construction, class coding, correlated predictors, or the absence of clinically verified biomarkers. The authors recommend that these patterns be investigated in clinically characterised datasets before any mechanistic conclusions are drawn.
The framework should currently be regarded as a modular proof-of-concept, because its binary and multiclass stages were trained on separate datasets that may differ in population, variables and collection methods.
Future work, the authors suggest, should use a single training dataset containing both diabetes status and clinically adjudicated subtype labels, including verified pancreatic and autoimmune markers rather than derived variables. External validation in larger and more diverse clinical cohorts would be needed to improve generalisability. Ethical and data privacy concerns would also need to be addressed before any AI-based model of this type could be translated into clinical screening or decision-support settings.
CCH insight
Studies like this one arrive faster than most clinicians can appraise them, and the gap between a promising accuracy figure and a tool that is safe to use in practice is wide. Knowing how to interrogate that gap is now a core professional skill.
AI Essentials for Primary Care is a 100% online, CPD-accredited short course providing 3.5 CPD hours and a Certificate of Completion. It equips the whole primary care team to evaluate AI tools against NHS standards, recognise when AI output should be questioned, and apply the SAFER Evaluation Framework in day-to-day practice. No technical background is required.
Explore AI Essentials for Primary Care →
Read More
Telemedicine in Nursing Homes Did Not Cut Hospital Admissions, German Trial Finds
Key Takeaways:
- A large cluster-randomised trial across 24 nursing homes in western Germany found no statistically significant reduction in hospital admissions or total days spent in care following an intersectoral, telemedicine-based intervention.
- Researchers tested 1,260 separate model specifications; around two-thirds pointed to a numerical trend towards fewer admissions, but none reached statistical significance (P < .05).
- The authors attribute the null result partly to external shocks, staffing pressures, limited GP engagement and short adaptation windows, and recommend narrower outcome measures and simpler, automated technology in future.
What the study set out to test
A prospective, multicentre cluster-randomised trial has concluded that introducing an intersectoral, telemedicine-based model of care into nursing homes did not produce a statistically significant reduction in hospital admissions among residents.
The research was led by John Grosser, Sophie Pauge, Birthe Aufenberg and Prof. Dr. Wolfgang Greiner of the Department of Health Economics and Health Care Management at Bielefeld University. They worked alongside Miriam Hertwig, Dr. med. Jenny Unterkofler, Dr. med. Christian Hübel and Prof. Dr. med. Jörg Christian Brokmann from the Department for Acute and Emergency Medicine at University Hospital RWTH Aachen, in collaboration with Dr. med. David Brücken of Rhine-Meuse Hospital Würselen and the Optimal@NRW Research Group.
The findings, published in JMIR Aging, evaluate the Optimal@NRW project as it was rolled out across 24 nursing homes in western Germany between May 2021 and April 2023.
The problem the intervention was designed to solve
Optimal@NRW was built around two well-documented pressures in long-term care: non-emergency hospital admissions that could plausibly have been managed in place, and persistent resource shortages across the sector. Transfers to hospital are disruptive for people living in nursing homes, costly for the wider system, and in a meaningful proportion of cases potentially avoidable if clinical assessment and decision support can be brought to the resident rather than the resident to the hospital.
Inside the model of care
The intervention combined four components intended to work as a single, joined-up pathway:
- A 24/7 telemedical consultation centre, giving nursing staff round-the-clock access to remote clinical input.
- Mobile non-physician medical assistants, able to attend the home and carry out assessments in person.
- A virtual emergency hub, coordinating escalation decisions across settings.
- A software-based early warning system for vital signs, designed to flag deterioration before it became acute.
Crucially, the model was intersectoral by design: it was meant to link the nursing home, emergency medicine and primary care rather than sit within any one of them.
A deliberately exhaustive statistical approach
Rather than relying on a single headline model, the research team used specification curve analysis to test how robust any effect was to analytical choices. They evaluated 1,260 distinct mixed-effects regression model specifications, drawing on both primary data collected during the trial and statutory health insurance claims data, with hospitalisation rates and total days spent in care as the outcomes of interest.
The result was consistent across that curve. Roughly two-thirds of the model variations indicated a numerical trend towards reduced hospital admissions, but not one of the 1,260 specifications demonstrated a statistically significant intervention effect at the conventional threshold (P < .05). In other words, the direction of travel was mildly encouraging, but the evidence did not support a claim that the intervention worked.
Why the intervention may not have delivered
The authors are candid that several practical and contextual factors are likely to have compromised the intervention’s chances of success.
External disruptions. The trial period coincided with severe regional flooding in western Germany and with ongoing COVID-19 pandemic restrictions. Both disrupted day-to-day operations in participating facilities and, importantly, distorted baseline hospitalisation rates against which any effect would have been measured.
Staff workload and usability. The model asked a great deal of nursing teams already contending with severe labour shortages. Complex, multi-component tasks – daily manual recording of vital signs among them – added meaningful operational stress rather than relieving it. A digital system that increases the documentation burden on staff is, in practice, competing with the very work it is meant to support.
Physician integration. Engaging general practitioners directly within the telemedical framework proved difficult. Because GP involvement was central to the intersectoral logic of the intervention, that gap limited how far the programme could genuinely connect primary care with the nursing home and the emergency pathway.
Short adaptation windows. Intervention phases ran for between 6 and 15 months per group. The authors suggest this may simply have been too short for staff to embed unfamiliar digital workflows into routine practice, particularly given the competing pressures above.
What the researchers recommend next
The team’s conclusions are constructive rather than dismissive of telemedicine in long-term care. They recommend that future digital health interventions in this setting should:
- Target specific, avoidable admission metrics rather than overall hospitalisations, which are influenced by too many factors outside the intervention’s reach to serve as a sensitive outcome measure.
- Allow extended implementation phases, giving teams realistic time to adapt to new digital workflows.
- Favour simplified, automated solutions such as wearable monitoring devices, reducing the manual data entry burden on nursing staff.
- Pursue deeper structural integration with general practitioners, so that primary care is built into the pathway rather than invited to join it.
What this means for practice
The wider lesson here is one that recurs across digital health evaluation: the technology itself is rarely the binding constraint. Implementation conditions – staffing capacity, workflow design, clinical buy-in and the length of time teams are given to adapt – tend to determine whether a well-conceived tool produces measurable benefit. Practitioners who are asked to assess, adopt or lead on digital tools increasingly need a framework for judging fit and feasibility, not just functionality, which is the ground covered by CPD-accredited training such as CCH’s AI Essentials for Primary Care: Tools, Ethics and Everyday Applications.
For services considering remote monitoring or telemedical support in care homes, the Optimal@NRW findings are a useful corrective. They suggest that ambition should be matched by realism about what frontline teams can absorb, and that outcome measures should be chosen precisely enough to detect an effect if one exists.
CCH insight
Digital tools are arriving in primary and community care faster than most teams can evaluate them. AI Essentials for Primary Care: Tools, Ethics and Everyday Applications is a CPD-accredited short course covering how to appraise digital and AI-enabled tools, work within governance requirements and get reliable results in everyday practice. It carries 3.5 CPD points and counts towards appraisal and revalidation.
Explore AI Essentials for Primary Care →
Source: JMIR Aging
Read More
AI Calorie Tracking Apps: Convenient, Popular and Consistently Inaccurate
Key Takeaways:
- Four popular photo-based calorie apps underestimated meal energy by 250 to 345 calories and fat by around 30 grams – roughly a third in both cases.
- Accuracy varied: higher-calorie meals fared better than lower-calorie ones, and carbohydrates were estimated more consistently than other macronutrients.
- Ketogenic meals proved hardest to assess, because their high fat content is consistently underestimated.
Convenience that comes with a margin of error
Advances in artificial intelligence have changed how many people record what they eat. Rather than weighing ingredients or searching a database entry by entry, a person can now photograph a plate of food and let an app estimate its nutritional content in seconds. The convenience is obvious. The accuracy, according to new research, is rather less reliable.
A study conducted at the National Institutes of Health (NIH) Clinical Center compared four popular photo-based apps against meals prepared under tightly controlled laboratory conditions. All four underestimated both calories and fat by approximately a third.
How photo-based calorie tracking works
Photo-based calorie tracking uses AI image recognition to identify the foods present in a photograph of a meal and to estimate the portion sizes on the plate. Those identifications and estimates are then matched against nutrition databases, which the app uses to calculate the energy and macronutrient content of the meal.
The appeal for people managing their weight or monitoring their intake for other health reasons is that the process removes several steps of manual data entry. The trade-off is that the app is making two judgements at once – what the food is, and how much of it there is – before any nutritional calculation begins.
“Photo-based calorie tracking apps are very popular, especially for people trying to manage their health or lose weight,” said Aaron Hengist, a postdoctoral visiting fellow with the Intramural Program of the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), part of the National Institutes of Health. “However, the accuracy of many of these apps has not been thoroughly evaluated. Our study helps address this question by looking at whether these apps can reliably estimate calories.”
A metabolic kitchen as the reference standard
The research forms part of a larger diet study at the NIH Clinical Center examining how the body processes nutrients when a person follows either a low-carbohydrate (ketogenic) diet or a standard diet.
Meals for that clinical trial are prepared in a controlled metabolic kitchen – a research kitchen in which every ingredient is weighed to the nearest 0.1 gram. That level of precision gave the investigators something unusual: a set of real, plated meals whose exact nutritional composition was already known.
The researchers took standardised photographs of 102 meals prepared for the diet study and ran the images through four apps: MyFitnessPal, LoseIt!, CalAI and Appediet.
“By using meals prepared in a tightly controlled metabolic kitchen, we were able to compare the apps’ estimates against a precise reference,” said Hengist. “This kind of direct, high-quality comparison hasn’t been available before.”
What the analysis found
Across the 102 meals, all four apps underestimated energy content by approximately 250 to 345 calories on average. Fat was underestimated by around 30 grams. In percentage terms, both calories and fat came in roughly a third below the true values recorded in the metabolic kitchen.
For a person using an app to guide daily intake, an error of this size is not trivial. A consistent shortfall of 250 to 345 calories per meal, repeated across a day, would produce a substantially inaccurate picture of overall energy intake – and would do so in the direction least helpful to someone trying to reduce it.
Where the apps performed better
The findings were not uniformly negative. The analysis showed that MyFitnessPal and LoseIt! estimated the energy content of higher-calorie meals more accurately than lower-calorie meals. All four apps also estimated carbohydrates more consistently than the other macronutrients, suggesting that carbohydrate-containing foods may be easier for image recognition systems to identify and quantify than fats in particular.
Hengist was direct about the practical implication for people using these tools without adjusting the app’s output.
“People using a photo-based tracking app without adjusting the portions or entering the amounts of food should take the results with a grain of salt,” said Hengist. “These apps tend to underestimate calories, especially from fats, so what they actually ate is likely higher than what the app shows.”
Ketogenic meals pose a particular challenge
After completing the initial analysis, the researchers extended the work to more than 200 additional meals in order to understand what factors influence app accuracy.
Their early results suggest that the apps struggle more with meals forming part of a low-carbohydrate ketogenic diet. The likely explanation is straightforward: these meals derive a large proportion of their energy from fat, and fat is precisely the macronutrient the apps most consistently underestimate.
This has implications for anyone supporting people who follow ketogenic or other high-fat dietary patterns, whether for weight management, metabolic health or the management of specific conditions. The tracking tool a person is relying on may be least accurate in exactly the dietary context where fat intake matters most.
For healthcare professionals who regularly review food diaries or app exports during weight management consultations, findings of this kind reinforce the value of structured training in dietary assessment. The College of Contemporary Health’s CPD-accredited Nutrition and Weight Management Essentials short course covers how dietary intake is assessed in practice, the limitations of self-reported data, and how to have constructive conversations with people about what and how much they are eating.
Improving accuracy in the real world
The investigators do not conclude that photo-based tracking should be abandoned. Their view is that combining photo-based features with more traditional methods of measuring diet quality could improve the real-world accuracy of calorie-tracking apps. In practical terms, that means treating the photograph as a starting point rather than a finished record – confirming what the app has identified, adjusting portion sizes, and entering quantities where they are known.
Olivia Charles, a postbaccalaureate intramural research training fellow at NIDDK, will present the findings at NUTRITION 2026, the flagship annual meeting of the American Society for Nutrition, held 25–28 July in National Harbor, Maryland, just outside Washington, D.C. As with research presented at scientific meetings generally, the results should be regarded as preliminary until they appear in a peer-reviewed publication.
For people using these apps day to day, the practical message is a modest one. A photograph is a useful prompt and a low-friction way to build a habit of recording intake. It is not, on the current evidence, a measurement.
CCH insight
Digital tools are increasingly part of how people monitor their diet, but their outputs need to be interpreted rather than accepted at face value – particularly where fat intake or high-fat dietary patterns are involved.
The College of Contemporary Health’s Nutrition and Weight Management Essentials CPD short course equips healthcare professionals with a working understanding of dietary assessment, macronutrient composition and evidence-based weight management, including how to interpret self-reported and app-generated intake data in clinical conversations.
Explore Nutrition and Weight Management Essentials
Source: EurekAlert!
Read More