

Obesity-Linked Lipids Drive Aggressive Breast Cancer Growth in Mouse Models
Key Takeaways:
- New research from the University of Utah reveals that lipids – fat molecules elevated in people living with obesity – can accelerate tumour growth in aggressive forms of breast cancer.
- The findings suggest that lipid-lowering therapies may slow cancer progression and that high-fat diets such as ketogenic regimens may worsen outcomes in some patients.
- Researchers caution that weight loss without addressing lipid levels is insufficient protection against obesity-associated cancers like triple-negative breast cancer.
Lipids identified as key driver in obesity-related breast cancer
A new study from the University of Utah’s Huntsman Cancer Institute (HCI) has found that lipids, a hallmark of obesity, play a significant role in fuelling tumour growth in an aggressive form of breast cancer. The research, funded by the National Cancer Institute and conducted using preclinical mouse models, highlights how lipid metabolism may be a crucial therapeutic target for individuals living with obesity who have or have survived breast cancer.
The findings suggest that breast cancer patients and survivors with obesity could benefit from therapies that lower lipid levels. Conversely, high-fat dietary approaches, such as the ketogenic diet, may have unintended adverse effects by increasing lipid availability to cancer cells.
“The key here is that people have underestimated the importance of fats and lipids in the all-encompassing term that is obesity,” explained Dr Keren Hilgendorf, assistant professor of biochemistry and investigator at HCI. “But our study shows that breast cancer cells are really addicted to lipids, and the abundance of lipids in patients with obesity is one of the reasons that breast cancer is more prevalent and more aggressive in these patients.”
Focus on triple-negative breast cancer
The study focused on triple-negative breast cancer (TNBC) – a fast-growing and difficult-to-treat subtype that lacks receptors for oestrogen, progesterone, and HER2. TNBC is more common in women under 40 and in Black women, and it accounts for approximately 10 to 15 per cent of all breast cancer cases. This form of cancer is particularly prone to recurrence and metastasis.
A high level of lipids in the blood, known as hyperlipidaemia, is a frequent feature of obesity. Dr Hilgendorf and her colleagues, Dr Amandine Chaix and Dr Greg Ducker, both from HCI, examined how lipid levels influence tumour growth using specialised mouse models.
Lipid levels alone drive tumour growth
The researchers used two sets of models: one group of mice was fed high-fat diets, while another was genetically engineered to develop hyperlipidaemia without other typical markers of obesity, such as elevated blood glucose or insulin levels. In both cases, tumours grew faster when lipid levels were high.
“The idea is that lipids, which form the surface membrane of the cell, are like building blocks,” explained Dr Chaix, assistant professor of nutrition and integrative physiology. “If a cell receives the signal to proliferate and more building blocks are available, the tumour is going to grow more easily. We see that a high amount of lipids enables this proliferation.”
Importantly, when lipid levels were lowered – even in the presence of high glucose and insulin – breast cancer cell growth slowed down.
Potential implications for treatment and prevention
While the research was conducted in mice, the results point to potential therapeutic strategies for people with obesity and breast cancer.
“We think this has therapeutic implications, because if you could just lower the lipids – which we already know how to do in patients, for example, with lipid-lowering medication – that could be a way to decelerate breast cancer growth,” said Dr Hilgendorf. “If we can target these high levels of fat in the blood, the cancer sufferers, because the lipids are no longer feeding the cancer. But while our results in mice were striking, there are clear limitations in directly projecting these findings onto human patients. More research using human samples and patients will be necessary to confirm our hypotheses.”
Rethinking weight management in cancer care
These findings may also influence how clinicians guide people with obesity and breast cancer in managing their weight. While weight loss is commonly recommended to reduce recurrence risk, there is limited guidance on the best dietary approaches.
Some individuals turn to ketogenic diets, which are high in fat and low in carbohydrates, to induce ketosis – a state where the body uses fat rather than carbohydrates for energy. However, the new findings raise concerns about such diets in this patient group.
“For patients who are diagnosed with breast cancer and have an elevated BMI [body mass index], we would advise them to consult their physician and develop a weight-loss plan as part of their treatment,” said Dr Ducker, assistant professor of biochemistry. “If you have high cholesterol levels to start with, think about a weight-loss plan or potential pharmaceuticals that could lower your lipid levels. As our study shows, diets like keto that are very high in fat can have serious unintended side effects – even causing the tumour to grow.”
Beyond breast cancer: Broader implications
The research team believes that lipid-driven tumour growth may not be limited to breast cancer alone. Elevated lipid levels could also contribute to tumour progression in other cancers linked to obesity, such as ovarian or colorectal cancers.
The next stage of the research will investigate how anti-lipid drugs could improve the effectiveness of chemotherapy and explore the mechanisms through which lipids feed cancer cells.
Dr Chaix, Dr Ducker and Dr Hilgendorf emphasised that their results apply specifically to triple-negative breast cancer, and that ketogenic diets might still hold benefits for other forms of cancer. Nevertheless, their findings underscore the need for careful, evidence-based dietary guidance for people with obesity affected by cancer.
Read More
Precision Medicine Poised to Redefine Obesity Prevention and Treatment
Key Takeaways:
- Researchers at the Pennington Biomedical Research Center highlight how precision medicine could revolutionise the prevention, diagnosis, and treatment of obesity by tailoring interventions to an individual’s biology and environment.
- Significant barriers remain, including limited large-scale clinical trials, underrepresentation of diverse populations, and challenges in integrating personalised tools into clinical practice.
- Experts call for robust biomarkers, inclusive research, and policy support to make precision obesity care accessible and evidence-based.
A blueprint for personalised obesity care
A new report led by researchers at the Pennington Biomedical Research Center underscores the rapidly growing potential of precision medicine to transform how obesity is prevented, diagnosed, and treated. Published in Obesity in September, the paper titled “Precision Prevention, Diagnostics and Treatment of Obesity” brings together insights from the recent Pennington–Louisiana Nutrition Obesity Research Center (NORC) scientific workshop.
The workshop, held in April 2024, convened experts to review evidence on tailoring obesity interventions to a person’s unique biological, behavioural, environmental, and social characteristics. The resulting report presents both the opportunities and obstacles in implementing precision-based strategies in obesity care.
Understanding the multifactorial nature of obesity
The authors emphasise that obesity is not a one-size-fits-all condition. Instead, it is shaped by a complex interplay of factors including genetics, epigenetics, metabolic phenotypes, microbiome composition, and environmental exposures. These elements influence why individuals gain or lose weight differently and why some respond better to certain interventions than others.
The review highlights how understanding these factors could enable clinicians to identify subgroups of people with obesity who would benefit from specific preventive or therapeutic strategies. This approach marks a shift from broad public health recommendations towards tailored, data-driven care.
Diagnostic innovation: Towards greater precision
The report calls for improved diagnostic tools—including the development of reliable biomarkers, imaging technologies, and phenotypic classifications—to better characterise the different subtypes of obesity and related risk profiles.
By accurately identifying an individual’s obesity phenotype, clinicians may be able to predict treatment response more effectively and target interventions that align with a person’s unique biology and lifestyle. Such advances could help move beyond the current trial-and-error approach in weight management.
Treatment personalisation and the path ahead
Emerging research indicates that personalising diet, physical activity, pharmacotherapy, and behavioural interventions according to an individual’s biological and psychosocial characteristics may improve both efficacy and long-term sustainability of outcomes.
However, the authors caution that while enthusiasm for precision-based treatment is growing, more robust clinical evidence is essential before these approaches can be fully integrated into standard care.
“Despite tremendous interest in precision-based treatment, the field is still relatively young,” said Dr Corby Martin, Co-Chair of the symposium and Director of the NORC Human Phenotyping Core. “We need rigorous clinical trials to empirically determine if precision treatment is indeed better than current practices. Unfortunately, few such trials exist, and those that do are not always supportive.”
Persistent gaps and barriers
The report identifies several key challenges hindering progress in precision obesity medicine:
- Limited large-scale clinical trials validating precision approaches.
- Insufficient diversity in study populations, leading to reduced generalisability of findings.
- Inadequate cost-effectiveness data, making implementation difficult within healthcare systems.
- Integration challenges when introducing precision tools into routine clinical settings.
Addressing these barriers will be essential for translating the promise of precision medicine into meaningful clinical and public health outcomes.
Recommendations for future research and policy
To advance the field, the authors recommend:
- Conducting diverse and inclusive research to ensure results are representative across ethnicities, genders, and socioeconomic groups.
- Developing and validating robust biomarkers and imaging tools for more accurate diagnosis and monitoring.
- Running comparative effectiveness trials to determine whether precision interventions outperform current standard treatments.
- Implementing programmes and policies that make precision obesity care both accessible and affordable.
The report suggests that precision-based approaches could enhance obesity prevention by identifying people at risk earlier and tailoring lifestyle or environmental interventions to reduce progression. Moreover, by customising treatment to a person’s biological and behavioural profile, clinicians could minimise side effects, avoid ineffective treatments, and improve outcomes.
A continuing commitment to obesity research
For more than 25 years, the Pennington–Louisiana Nutrition Obesity Research Center (NORC) has convened over 100 scientists annually to explore emerging topics in obesity and nutrition science.
“Supporting 1.5-day workshops such as the ‘Precision Prevention, Diagnostics, and Treatment of Obesity’ brings top scientists and clinicians from around the world to Pennington Biomedical,” said Dr Leanne Redman, NORC Director, LPFA Endowed Chair in Nutrition, and Associate Executive Director for Scientific Education. “These reports provide a blueprint for the current state of the science and avenues for future research.”
Building a collaborative future
Dr John Kirwan, Executive Director of Pennington Biomedical, commended the team’s contribution:
“This team’s efforts in advancing precision medicine to diagnose, prevent, and treat obesity are truly commendable. At Pennington Biomedical, our work is built on strong partnerships across Louisiana and throughout the United States, strengthened through centres and institutes like the Pennington–Louisiana NORC. We are proud to collaborate with leading research institutions, universities, and healthcare systems nationwide to advance obesity research.”
As the science of precision medicine matures, the report provides a clear framework for how personalised approaches may one day redefine obesity prevention and treatment, improving outcomes for individuals and populations alike.
CCH insight:
Precision approaches to obesity prevention and treatments could massively improve outcomes for people with, or at risk of, obesity. The complex nature of the condition, with its broad range of biological, behavioural, psychological, social and environmental determinants and risk factors, means every patient is unique and requires a personalised intervention. However, this complexity of obesity also makes it difficult to characterise an individual’s obesity phenotype and predict responses to interventions – so there is still a long way to go, a lot more research is needed.
Read More
Exercise Shown to Reduce Artery Hardening After Weight Loss in Adults With Obesity
Key Takeaways:
- Regular exercise after weight loss significantly reduces inflammation and improves blood vessel health in adults living with obesity.
- The GLP-1 receptor agonist liraglutide helped participants maintain weight but did not show the same protective effects against artery hardening.
- Researchers emphasise exercise as an essential factor for maintaining cardiovascular health after weight reduction.
Exercise and heart health after weight loss
Maintaining weight loss through regular exercise, rather than relying solely on the glucagon-like peptide-1 receptor agonist (GLP-1RA) liraglutide, appears to protect against atherosclerosis in adults living with obesity, according to new research from the University of Copenhagen. Atherosclerosis—hardening and narrowing of the arteries due to inflammation and fat deposits—is a major underlying cause of cardiovascular disease (CVD).
The findings were presented at the Annual Meeting of the European Association for the Study of Diabetes (EASD) 2025 in Vienna (15–19 September).
“Our findings reveal that regular exercise is crucial to helping people living with obesity get the full cardiovascular benefits after a substantial weight loss,” said Dr Rasmus Sandsdal, lead author of the study from the University of Copenhagen, Denmark.
Understanding the risk
Cardiovascular disease remains the leading cause of death globally. It often begins with atherosclerosis, in which chronic inflammation and lipid accumulation cause the arteries to stiffen and narrow. If left unchecked, these plaques can rupture and trigger life-threatening events such as heart attacks and strokes.
Obesity contributes to chronic low-grade inflammation and endothelial dysfunction—a condition in which blood vessels lose their ability to contract and relax properly—both of which accelerate atherosclerosis.
While both exercise and GLP-1RAs are known to lower cardiovascular event risk in people with obesity, their specific effects on the development of atherosclerosis during weight loss maintenance have remained unclear—until now.
The study design
The Danish research team conducted a randomised placebo-controlled trial involving 215 adults aged 18–65 years (63% female) living with obesity (BMI 32–43 kg/m²) but without diabetes or other serious chronic conditions.
All participants began an eight-week low-calorie diet (800 kcal per day) using the Cambridge Weight Plan. Of these, 195 participants who achieved at least a 5% reduction in body weight (average loss of 12% or 13.1 kg) entered a one-year maintenance phase. They were randomly assigned to one of four groups:
- Exercise (150 minutes/week of moderate-to-vigorous activity) plus placebo
- Liraglutide treatment (3.0 mg per day)
- Exercise combined with liraglutide
- Placebo only
Researchers measured several key biomarkers at three points—before dieting, at the start of weight maintenance, and after one year. These included inflammatory markers (interleukin-6 [IL-6] and interferon-γ [IFN-γ]), endothelial function markers (intercellular adhesion molecule [ICAM-1], vascular adhesion molecule [VCAM-1], and tissue plasminogen activator [tPA]), and carotid artery intima-media thickness [cIMT], an indicator of arterial wall health measured by ultrasound.
Exercise reduced inflammation and improved arterial health
After one year, participants in both the exercise and liraglutide groups successfully maintained their weight loss. However, significant differences emerged in their cardiovascular health profiles.
Those who exercised—whether or not they also received liraglutide—had notably lower levels of inflammatory biomarkers compared with non-exercising participants. On average, IL-6 levels were 21% lower, and IFN-γ levels were 27% lower.
Exercise also had a favourable effect on endothelial function, reflected in a 6% reduction in VCAM-1, 8% reduction in ICAM-1, and 12% reduction in tPA compared to those who did not exercise. Moreover, carotid artery thickness decreased by an average of 0.024 mm, indicating reduced arterial hardening.
In contrast, treatment with liraglutide alone did not yield any measurable improvements in inflammatory or endothelial biomarkers, nor did it affect carotid artery thickness.
“Regular exercise seems to confer a protective effect against the development of atherosclerosis in people trying to maintain weight loss,” said Dr Sandsdal. “Since both exercise and GLP-1RA treatment were successful at keeping weight off, it seems that exercise plays an important role in mitigating cardiovascular risk factors in a weight-independent manner.”
Implications for long-term health
Exercise offers multiple benefits beyond weight control, including improvements in body composition, cardiorespiratory fitness, and metabolic health. Together, these contribute to better long-term cardiovascular outcomes.
“The most important message from our findings is that, for those trying to maintain weight loss, exercise is crucial in improving long-term health,” said Professor Signe Sørensen Torekov, corresponding author from the University of Copenhagen. “Given the substantial societal and economic costs of obesity-related cardiovascular disease, these findings underscore regular exercise as a critical component of weight management and heart health.”
Study limitations and future research
The authors acknowledged several limitations. The study’s sample size was relatively small, and adherence to structured exercise in real-world conditions may be lower than in a supervised trial setting.
Future studies, they suggested, should explore longer-term interventions and evaluate newer GLP-1 receptor agonists—potentially more potent than liraglutide—in combination with consistent exercise to assess whether similar or enhanced cardiovascular benefits can be achieved.
CCH insight:
We have long known that exercise is important for cardiovascular health, so the results of this study should not be a surprise – exercise provides cardiovascular benefits whether or not you are taking a GLP-1 medication. It is also important to remember that GLP-1 receptor agonists are meant to be taken as an adjunct to a healthy diet and lifestyle, including exercise. This is not just about weight management, but also about maximising health benefits and minimising the risk of developing diseases associated with obesity – such as cardiovascular disease.
Read More
Severe Obesity Accelerates Lung Ageing by Altering Tissue Structure, Study Finds
Key Takeaways:
- Researchers at the University of Bonn have shown that severe obesity causes structural and molecular changes in lung tissue that mimic those of natural ageing.
- Obesity leads to the accumulation of fat within lung connective tissue cells, disrupting their normal function and reducing lung elasticity.
- These findings help explain why people living with obesity often experience breathing difficulties and may face a higher risk of lung-related complications.
Obesity found to accelerate ageing in the lungs
A research team led by Professor Dr Veronika Lukacs-Kornek from the ImmunoSensation2 Cluster of Excellence at the University of Bonn and the Institute for Molecular Medicine and Experimental Immunology (IMMEI) at the University Hospital Bonn (UKB) has discovered that severe obesity causes the lungs to age prematurely. The findings, published in Cell Reports, shed new light on how excessive body weight affects lung function and structure at the molecular level.
The study explored how the lungs respond to nutritional challenges associated with obesity, revealing that excess body fat significantly remodels the extracellular matrix (ECM) – the protein-based “scaffolding” that provides the lungs with their shape, strength, and stability. These alterations in lung architecture closely resemble those typically observed during the natural ageing process, suggesting that obesity accelerates the biological ageing of lung tissue.
Multi-omics analysis reveals profound structural changes
To investigate these effects, the researchers employed state-of-the-art multi-omics techniques – a set of advanced tools that allow for the simultaneous study of proteins, lipids, and genes. This integrative approach enabled the team to map how obesity influences the lungs at multiple biological levels.
By combining molecular analyses with microscopic imaging and functional experiments that tested how lungs perform, the team was able to capture a comprehensive picture of obesity’s impact. They compared the lungs of obese and lean mice, examined human lung fibroblasts (connective tissue cells), and studied the overall composition of lung tissue to identify both molecular and functional differences.
Fat accumulation and loss of elasticity in lung tissue
The results showed that in obesity, lung fibroblasts – the cells responsible for maintaining the connective tissue – begin to accumulate fat, becoming more mobile and displaying early signs of premature ageing. At the same time, the matrisome, which refers to the entire collection of ECM proteins, undergoes significant changes.
These changes disturb the delicate balance of protease inhibitors, enzymes that regulate tissue maintenance and repair. As a consequence, the lungs become less elastic and more prone to stiffness. This reduced elasticity helps explain why people living with obesity often experience shortness of breath and other respiratory difficulties.
“Interestingly, these changes are similar to those normally seen in older people – pointing to obesity as a driver of accelerated lung ageing,” the authors noted.
Overcoming complex research challenges
Studying the lung’s connective tissue presented major technical challenges. The fibroblastic stroma – the supportive framework of the lungs – comprises numerous cell types with highly specialised roles, making it difficult to isolate and analyse. Furthermore, the extracellular matrix itself is notoriously complex: many of its proteins are insoluble and possess intricate structures that resist standard laboratory analysis.
To address this, the team had to develop novel analytical methods that could overcome these limitations and enable the simultaneous study of multiple molecular components within the tissue. This innovative approach has allowed researchers to better understand how obesity-induced changes at the cellular level translate into functional impairments in lung performance.
Implications for understanding obesity-related lung disease
The study provides compelling evidence that obesity accelerates biological ageing processes in the lungs, underscoring the broader systemic impact of excess body weight beyond metabolic and cardiovascular complications.
By demonstrating that obesity alters both the composition and function of lung tissue, the findings open new avenues for exploring how weight management and metabolic interventions might help preserve lung health and mitigate premature ageing in people living with obesity.
CCH insight:
This is an interesting study. It shows that shortness of breath in people with obesity is not simply a case of poor cardiorespiratory fitness or due to mechanical difficulties due to accumulation of adipose tissue in the chest – it actually involves structural changes to lung tissue, similar to biological aging. It would be interesting to compare the lung tissue of people with obesity who have a sedentary inactive lifestyle with that of people with obesity who are active and physically fit, to see if exercise and better cardiorespiratory fitness can prevent these tissue changes and premature aging of the lungs.
Read More
Many People with Severe Obesity Face Medical Discrimination, Study Finds
Key Takeaways:
- A new study reveals that over 40% of clinics in the United States refused to schedule an appointment for a hypothetical patient with severe obesity.
- More than half of practices surveyed lacked the basic facilities or equipment required to provide appropriate care to patients with a body mass index (BMI) of 60 or greater.
- Researchers warn that discrimination and inadequate resources may contribute to poorer health outcomes, including delayed cancer detection, among people living with severe obesity.
Widespread discrimination in clinical settings
People living with severe obesity frequently encounter discrimination and barriers when seeking medical care, according to a new study published in the Annals of Internal Medicine. Researchers reported that about 2 in 5 (41%) clinics refused to schedule an appointment for a hypothetical patient weighing 465 pounds.
One receptionist at an orthopaedic surgeon’s office stated: “We’ve reached our limit for bariatric patients at this site,” without offering further explanation.
The study highlights a critical issue in access to care: beyond outright refusals, more than half of clinics (52%) did not have the equipment or facilities necessary to provide basic medical care for patients with very high body weights. Severe obesity is defined as a BMI of 40 or higher, with extremely severe obesity considered a BMI of 60 or greater.
Lack of facilities and equipment
Many clinics lacked essential infrastructure, including examination tables or chairs that could safely support higher weights, wide enough doorways and hallways for patient mobility, and appropriately sized medical gowns.
Dr Tara Lagu, senior author of the study and adjunct lecturer of medicine and medical social sciences at Northwestern University Feinberg School of Medicine in Chicago, emphasised the harmful impact of such deficiencies:
“Patients living with severe obesity are likely already struggling with shame and difficulty navigating the world. To tell a patient that they can’t be examined on a table, or can’t wear a gown, or need to stand during an appointment makes what should be a safe place and the experience of seeing a doctor humiliating and degrading. We need to acknowledge, as a profession, that all people deserve better than this.”
Affected population and health risks
According to the researchers, approximately 1 in every 270 Americans – close to 1 million adults – lives with extremely severe obesity (BMI ≥ 60). These individuals are two to three times more likely to experience significant health problems compared with the general population.
Despite this increased risk, previous studies have shown that people with obesity are less likely to receive preventive health services such as cancer screenings. Dr Lagu explained:
“Obesity affects cancer screenings, and failure to screen can result in later cancer detection. We’re always attributing worse outcomes in higher-weight patients to weight itself, but more and more studies are now pointing to worse care, lack of care or being care avoidant as possible reasons for these delays.”
Study design and findings
To investigate barriers to care, researchers used a “secret shopper” approach, in which callers attempted to schedule an appointment for a hypothetical patient weighing 465 pounds. They contacted 300 clinics across four metropolitan areas – Boston, Cleveland, Houston, and Portland, Oregon. The study covered five specialties: dermatology, endocrinology, obstetrics and gynaecology, orthopaedic surgery, and ear, nose, and throat (ENT).
Lead researcher Dr Molly Hales, a physician at University of Chicago Medicine, noted that the caller questions were intentionally designed to suggest possible urgent medical needs:
“We designed some of the questions our callers asked to be red flags for a receptionist to think, ‘I should really schedule this person,’ because the questions suggested the patient might have cancer and need an urgent workup.”
Despite this, only 59% of clinics overall were willing to schedule the appointment. ENT specialists were least likely to agree, with only 48% offering an appointment, while endocrinologists were most likely to accept and to have suitable facilities.
Humiliating workarounds
Even among clinics that agreed to see the hypothetical patient, around 1 in 6 (16%) suggested workarounds that could be humiliating, such as requiring the patient to stand during the exam or to use a sheet instead of a gown.
Dr Hales observed:
“Our numbers likely underestimate the magnitude of the problem. Likely, very few high-weight patients who are scheduling appointments know to even ask if they can be accommodated based on their weight, and they might be hesitant to ask these questions or advocate for themselves because of the social stigma.”
Potential solutions
The researchers highlighted that a Clinical Environment Checklist has been developed to guide outpatient clinics in ensuring they can provide appropriate care for patients with obesity. However, it has not been widely adopted.
Dr Hales noted:
“They designed the checklist to be used by general outpatient clinics and tested it in both primary care and subspecialty settings, so it’s a good resource for clinics in determining where there are opportunities for improvement.”
Read More
Green Tea Shows Significant Benefits for Glucose Metabolism and Muscle Health in Mice with Obesity
Key Takeaways:
- Green tea extract significantly improved insulin sensitivity, glucose tolerance, and muscle preservation in mice with obesity, even when they continued consuming a high-calorie diet.
- The study controlled for temperature effects, providing clearer evidence that green tea’s metabolic benefits are independent of cold-induced energy expenditure.
- Findings suggest a potential role for green tea as a safe, accessible adjunct to obesity treatment in humans, though exact dosing for people remains to be established.
Ancient beverage, modern research
Green tea, long valued for its medicinal and antioxidant properties, continues to attract scientific interest for its impact on metabolic diseases such as obesity and type 2 diabetes. A recent study led by Professor Rosemari Otton from the Interdisciplinary Graduate Programme in Health Sciences at Cruzeiro do Sul University in São Paulo, Brazil, offers new insights into how green tea affects metabolism.
Otton, who has dedicated over 15 years to the study of green tea, explained that her initial curiosity stemmed from the popular belief that green tea promotes weight loss. The findings of her latest research, published in Cell Biochemistry & Function, reinforce the potential of green tea as a therapeutic adjunct in managing obesity.
Study design and green tea administration
The research team first fed mice a high-calorie diet for four weeks, including both a fat-rich diet and a “cafeteria diet” to replicate a Western-style eating pattern. “We give them chocolate, filled cookies, dulce de leche, condensed milk… In other words, the same type of food that many people consume on a daily basis,” said Otton.
After this induction phase, the mice continued on the high-calorie diet for 12 weeks, with some receiving a standardised green tea extract at 500mg per kilogram of body weight via intragastric gavage. This method ensured precise dosing. “If we put it in water, for example, we’d have no way of knowing how much the animal actually ingested,” Otton explained.
For humans, this dose would equate to approximately 3 grams of green tea daily — roughly three cups. However, Otton cautioned that not all commercial products meet required standards:
“Ready-made tea bags do not always guarantee the quantity or quality of the compounds. The ideal for consumption would be to use standardised green tea extract, like those found in compounding pharmacies. This is a concentrated way of using the plant, with a guarantee of the presence of flavonoids, which are the health-beneficial compounds present in the green tea plant.”
Controlled conditions for reliable results
A distinctive feature of the study was the use of a thermoneutral environment at 28°C, eliminating confounding effects caused by chronic cold exposure. Mice are typically kept at around 22°C in animal facilities, a temperature that triggers energy expenditure to maintain body heat.
“Excessive cold activates compensatory regulatory mechanisms in the animals’ bodies, causing them to expend more energy to stay warm. This can mask the real effects of any substance,” Otton explained. “By maintaining thermoneutrality, we were able to see the effects of green tea in a ‘clean’ way, without environmental interference.”
A previous study published in European Journal of Nutrition (August 2022) found that obese mice treated with green tea lost up to 30% of their body weight — a reduction Otton described as highly significant:
“If a person loses 5% to 10% of their body weight, that’s already a lot. So this result in animals is very significant.”
Preservation of muscle health
One of the most striking findings of the latest study was the preservation of muscle fibre morphology. Obesity often leads to a reduction in muscle fibre diameter, but green tea helped maintain muscle structure.
“One way to assess muscle function is to look at fibre diameter. If it increases, we have more active muscle components. Green tea managed to maintain this diameter, showing that it protects muscle against the harmful effects of obesity,” Otton said.
Genetic and metabolic insights
The study also explored gene expression related to glucose metabolism. Green tea treatment enhanced the expression of genes such as Insr, Irs1, Glut4, Hk1, and Pi3k, all of which play a role in glucose uptake and utilisation in muscle tissue. Additionally, the activity of lactate dehydrogenase (LDH), an enzyme vital for glucose metabolism, was restored.
Otton noted that green tea appeared to have a selective effect:
“It makes obese animals lose weight but keeps lean animals at a balanced weight. This shows that the tea seems to need an environment with excess nutrients to act, which supports the hypothesis that it acts directly on fat cells.”
Synergy of bioactive compounds
Green tea contains dozens of bioactive compounds, and attempts to isolate them have proven less effective than using the whole extract.
“We’ve tried to separate these compounds and study their effects individually, but the whole extract is always more effective. There’s a synergy between the compounds that we can’t reproduce when they’re isolated,” Otton explained.
One mechanism under investigation involves adiponectin, a protein secreted by fat cells that regulates inflammation and metabolism. In mice genetically modified to lack adiponectin, green tea showed no effect — pointing to adiponectin as a key mediator of its benefits.
Translating findings to human health
Despite these promising findings, Otton cautioned that safe and effective doses for humans have yet to be established, owing to variability in extracts and individual responses. She stressed the importance of long-term, habitual consumption rather than expecting rapid results:
“The ideal is chronic consumption, as we see in Asian countries. In Japan, for example, people consume green tea every day, throughout their lives, and obesity rates are low. But this is different from drinking tea for five months and expecting a miraculous weight loss effect.”
Otton also emphasised the importance of accessible and safe treatment options:
“The idea is to have safe, natural, effective, and high-quality compounds. The Camellia sinensis plant offers this. We’re still studying all the compounds involved, but there’s no doubt that green tea, as a plant matrix rich in flavonoids, has important therapeutic potential.”
The road ahead
Finally, Otton underscored the need for caution when translating animal research to clinical practice:
“What we see in animals doesn’t always reproduce in humans. But if we want to make this translation to real life, we need to think about all the details, such as ambient temperature. It’s these precautions that increase the validity of our data. We’re far from having all the answers, but we’re getting closer and closer.”
Read More
Fasting may influence metabolism and immunity differently depending on body type, study finds
Key Takeaways:
- New research shows that people living with obesity respond differently to fasting compared to lean individuals, particularly in how their immune systems react.
- A 48-hour fasting study found that lean participants’ immune cells adapted by burning more fat, while those with obesity maintained higher levels of pro-inflammatory signals.
- Researchers say the findings highlight the complex interaction between nutrition, metabolism and immune function, and stress the need for further investigation.
Growing interest in fasting and ketogenic diets
Fasting has become a popular dietary trend, especially among those seeking to manage weight. Increasingly, fasting is paired with ketogenic or very low-carbohydrate diets, which aim to shift the body’s energy use from carbohydrates to stored fat, producing ketones as an alternative fuel source.
Dr Hashim Islam, Assistant Professor in the School of Health and Exercise Sciences at the University of British Columbia Okanagan (UBCO) and a member of the Centre for Chronic Disease Prevention and Management, explains that while fasting and low-carbohydrate diets can be beneficial, their effects are not uniform across all body types.
“These diet trends continue to grow in popularity. But our study found that people with obesity may respond to fasting differently than leaner individuals, especially in how their immune systems react,” says Dr Islam.
Fasting and immune health
Fasting has attracted significant attention in recent years, partly because of its coverage in mainstream media. Beyond public interest, scientists value fasting for its potential to alter metabolic processes in beneficial ways.
Lead author Dr Helena Neudorf notes that fasting forces the body to switch from burning glucose to burning fat, a process that produces ketones. “Fasting may improve health by changing metabolism to strengthen the immune system and reduce chronic inflammation, which is linked to many diseases,” she says.
However, the team was particularly interested in whether fasting has distinct effects on people living with obesity compared with lean individuals.
Study design and methods
To investigate, the researchers recruited participants with obesity and lean counterparts. Each group underwent a 48-hour fasting period, during which blood samples were collected before, during and after the fast.
The samples were analysed for hormones, metabolites, metabolic rate, inflammation markers and the activity of T cells – white blood cells that are crucial for fighting infections but can also drive chronic inflammation.
The study was a collaborative effort between Dr Islam’s group and Professor Jonathan Little’s research group at UBCO’s Centre for Chronic Disease Prevention and Management. The findings were published in iScience.
Key findings
The results indicated that fasting did not affect all participants equally.
- In people living with obesity: T cells remained more pro-inflammatory, continuing to produce inflammatory signals even after fasting. These participants also showed a smaller increase in ketones and lower levels of important chemical reactions associated with immune regulation, such as ketones binding to amino acids or proteins.
- In lean participants: Immune cells adapted more readily to fasting by shifting to fat metabolism. This led to a stronger movement towards a balanced, anti-inflammatory state compared with their counterparts living with obesity.
“We also found the immune cells in lean participants adapted to fasting by burning more fat. This didn’t happen in those living with obesity,” explains Dr Neudorf. “Overall, their shift toward a more balanced, anti-inflammatory state was weaker in this particular group.”
Implications and future research
The findings suggest that while fasting may carry health benefits, these benefits may be blunted in people living with obesity. Dr Islam stresses that the implications of this are not yet fully understood.
“People living with obesity may respond differently to an isolated two-day fast compared to those who are leaner, but we don’t yet know if this is good or bad,” he says. “Our study shows the complex relationship between nutrition, metabolism and immune function, and that more research is needed to see how fasting can be used as a therapeutic tool for people with different body types.”
CCH Insight
This study is a good reminder that there is no one diet that suits everyone. We are all biochemically unique, due to a range of personal factors such as genetics, the makeup of our gut microbiome and our state of health, so it is always a good idea to be skeptical about ‘shiny new diets’ that appear to be the answer for weight loss or longevity. In this study, fasting appears to benefit people of a healthy weight, but not those living with obesity. Considering that one of the keys to good health and maintaining a stable, healthy body weight is to adopt healthy dietary habits that works for you and you can sustain, it is arguable that regular fasting could be unhelpful for people with obesity, who may be prone to binges or irregular eating patterns.
Read More
Global study reveals obesity has overtaken being underweight among the world’s young
Key Takeaways:
- For the first time in recorded data, there are more children and adolescents living with obesity than those who are underweight, according to UNICEF.
- Nearly one in ten young people aged 5–19 years – around 188 million globally – are now affected by obesity, driven largely by the rise in consumption of ultra-processed foods.
- UNICEF is calling for urgent government action to protect children’s diets, restrict the influence of the ultra-processed food industry on policymaking, and make nutritious foods affordable and accessible.
A historic shift in global child health
For the first time, the number of children and adolescents worldwide living with obesity has surpassed the number who are underweight. This milestone, highlighted in a major study by UNICEF, underscores a profound transformation in global nutrition and public health.
The study found that approximately one in ten young people aged between 5 and 19 years – an estimated 188 million individuals – are now living with obesity. This represents a sharp increase compared with the early 2000s. Researchers attribute this shift primarily to the replacement of traditional diets with ultra-processed foods that are inexpensive, calorie-dense, and nutritionally poor.
Redefining malnutrition
Historically, malnutrition in children was almost synonymous with underweight and hunger. Today, the definition is broader, encompassing not only wasting and stunting but also the growing prevalence of overweight and obesity.
Children are classified as overweight when their weight significantly exceeds the healthy range for their age, sex, and height. Obesity is recognised as the more severe form of overweight and is associated with an elevated risk of type 2 diabetes, cardiovascular disease, and some cancers in later life.
Good nutrition throughout childhood – including adequate intake of fruit, vegetables, and protein – is vital for healthy growth, cognitive development, and mental wellbeing. Yet many of these traditional sources of nourishment are being replaced by foods laden with sugar, starch, salt, unhealthy fats, and artificial additives.
UNICEF’s Executive Director, Catherine Russell, warned that the dangers posed by this trend must not be underestimated. She described obesity as “a growing concern” that has significant implications for the health and development of children.
Rising obesity, declining underweight
The UNICEF-backed study, which analysed data from over 190 countries, highlights two diverging global trends. Between 2000 and 2022, the proportion of children aged 5–19 years who were underweight declined from nearly 13 per cent to 9.2 per cent. At the same time, obesity rates rose steeply from 3 per cent to 9.4 per cent.
This means that almost one in ten children worldwide is now living with obesity. When combining overweight and obesity, the figures are even more striking: one in five school-aged children and adolescents – around 391 million globally – is above a healthy weight.
Although underweight remains a pressing concern in children under the age of five, particularly in low and middle-income countries, obesity is increasingly the dominant nutritional challenge for those aged 5–19. The only regions where underweight still exceeds obesity are sub-Saharan Africa and South Asia.
Geographic hotspots and global distribution
The prevalence of childhood obesity is particularly acute in certain regions. Pacific Island nations have some of the highest rates, including Niue (38 per cent), the Cook Islands (37 per cent), and Nauru (33 per cent).
High-income countries are not exempt. In Chile, 27 per cent of 5–19-year-olds live with obesity, while in the United States and the United Arab Emirates the figure stands at 21 per cent.
“This double burden of malnutrition – the existence of both stunting and obesity in the same populations – requires targeted interventions,” Catherine Russell explained. “Nutritious and affordable food must be available to every child to support their growth and development. We urgently need policies that support parents and caretakers to access nutritious and healthy foods for their children.”
The call to action
The UNICEF report highlights the potentially devastating health and economic consequences of inaction. By 2035, the global economic burden of overweight and obesity is projected to exceed US$4 trillion (£2.95 trillion) per year.
To mitigate these risks, UNICEF has called upon governments to implement robust policies. These include:
- Restricting unhealthy foods – such as removing ultra-processed products from school canteens and regulating food labelling and marketing to children.
- Introducing fiscal measures – for example, taxing sugar-sweetened beverages and other unhealthy products, while incentivising healthier options.
- Encouraging reformulation – compelling food manufacturers to reduce unhealthy ingredients such as excess salt, sugar, and harmful fats.
- Safeguarding policy from industry influence – ensuring that ultra-processed food and drink producers are excluded from developing or implementing public health policy. Any lobbying efforts would need to be transparently reported.
A global imperative
The findings mark a pivotal moment in global health, emphasising the urgent need for a coordinated response. The steady replacement of traditional diets with ultra-processed foods has triggered a nutrition crisis that spans continents and income levels.
Without decisive policy action, the health outcomes for millions of children and the economic burden for societies will only worsen. UNICEF’s call is clear: protecting children’s diets from the pervasive influence of ultra-processed food industries and ensuring access to affordable, nutritious foods must become a global priority.
CCH Insight:
These statistics highlight an interesting phenomenon occurring in some developing countries, such as India, China and Nigeria. As these countries develop economically, they are grappling with the dual challenge of undernourished, underweight children in poor, mostly rural areas, and childhood obesity amongst the more affluent, who have adopted a western, processed food diet, mostly in urban areas. Due to the populous nature of these countries, global childhood obesity rates are likely to continue to rise for many years to come, unless a concerted effort is made to regulate food processing, as suggested by the authors. Unfortunately, the food industry is a very powerful lobby, that makes these kind of policies very difficult to adopt.
Read More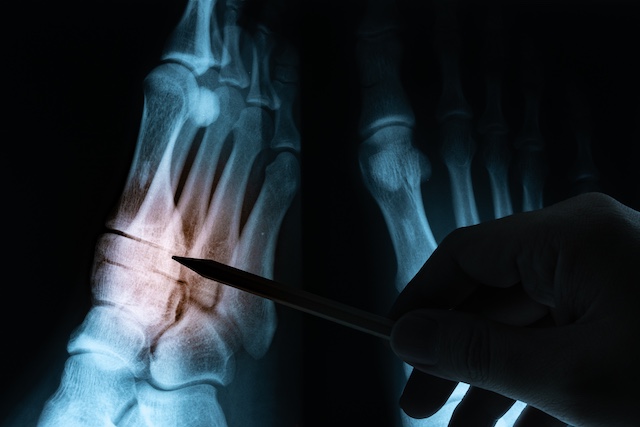
Large-scale study finds children with obesity face markedly higher risk of limb fractures
Key Takeaways:
- Children with obesity at the age of starting school have nearly a five-fold higher risk of bone fractures during childhood compared with children of a healthy weight.
- Analysis of almost 467,000 children in Catalonia showed obesity at age four was associated with a 70% higher risk of lower limb fractures and a 20% higher risk of upper limb fractures.
- Findings highlight the long-term health implications of obesity in the preschool years, reinforcing the need for early intervention and further research.
Growing concern over childhood obesity
The rising prevalence of childhood obesity is a major global public health challenge. It has already been linked to a wide range of conditions in later life, including cardiorespiratory disease, type 2 diabetes, and mental health disorders. Much of the research in this field has focused on obesity in older children and its consequences for adult health. Less is known about how excess weight in the preschool years influences immediate health outcomes during childhood and adolescence.
A new study, published in the Journal of Bone & Mineral Research and supported by the NIHR Oxford Biomedical Research Centre, sought to address this gap by examining whether obesity at the age of school entry is associated with an increased risk of fractures in later childhood.
Study aims and design
“The primary aim of the study was to determine if elevated body mass index (BMI) just before starting school at age 4 years was associated with an increased incidence of fracture in childhood,” explained Jennifer Lane, Versus Arthritis Clinical Research Fellow in Orthopaedic Surgery at the Nuffield Department of Orthopaedics, Rheumatology and Musculoskeletal Sciences and lead author of the paper. “We found that elevated body weight at the age of starting school increased the risk of breaking a bone later in childhood.”
To investigate this, the research team – consisting of scientists and doctors from the United Kingdom and Spain – analysed the anonymised health records of 466,997 children living in Catalonia. As part of routine healthcare check-ups before starting school, each child was weighed and measured, and their BMI calculated. The researchers then followed the health of these children until they reached 15 years of age, or until data were no longer available due to other reasons such as moving away.
Key findings
At baseline, 5.7% of the children were classified as overweight and 2.0% as having obesity according to their BMI. The results showed a clear link between higher BMI at preschool age and later fracture risk:
- Children with obesity at age four faced a 70% higher risk of lower limb fractures and a 20% higher risk of upper limb fractures compared with peers of a healthy weight.
- Children with overweight had a 40% higher risk of lower limb fractures and a 10% higher risk of upper limb fractures.
These findings underscore that excess body weight at the point of starting school is not only a predictor of long-term health risks but also increases vulnerability to fractures during the remainder of childhood.
Next steps and research implications
Jennifer Lane highlighted the importance of building on this work to understand the underlying biological and mechanical mechanisms: “More research is needed to further understand the mechanisms underlying this correlation. Our study adds to a body of work that supports further research into the role that pre-school obesity has in health problems in childhood and beyond.”
While the precise pathways are not yet fully understood, potential factors may include greater force exerted on bones during falls, differences in bone structure or density, or changes in physical activity patterns among children with overweight or obesity.
Broader significance
The study is one of the largest of its kind to investigate fracture risk in relation to BMI measured at preschool age. Its findings highlight the importance of early monitoring of weight and growth, as well as timely interventions that support healthy development before children enter formal education.
The evidence reinforces that obesity in the early years is not only a future risk factor for adult disease but also has immediate and tangible consequences for musculoskeletal health during childhood.
Read More
Obesity drives high rates of chronic disease in US adolescents and young adults
Key Takeaways:
- A new JAMA Pediatrics study found obesity is linked to a substantial proportion of chronic health conditions in US adolescents and young adults, with the highest impact seen in liver steatosis and type 2 diabetes.
- Among young adults with obesity, nearly 79% of type 2 diabetes cases were attributable to excess weight, while almost half of adolescent liver steatosis cases were linked to obesity.
- Researchers emphasise the need for early prevention and treatment strategies, including behavioural, surgical, and pharmacological interventions, to mitigate long-term health and economic consequences.
Rising prevalence of obesity and chronic disease
The prevalence of obesity among adolescents and young adults in the United States continues to rise and is closely linked with a growing burden of obesity-related conditions (ORCs). A study recently published in JAMA Pediatrics has provided one of the most comprehensive analyses to date, showing that obesity accounts for a substantial share of several chronic health conditions in this population.
Researchers conducted a cross-sectional analysis using pooled data from the National Health and Nutrition Examination Survey (NHANES) between 2013 and 2023. The study population included 4199 adolescents aged 12–17 years and 3200 young adults aged 18–25 years. These participants represented approximately 56 million people nationwide. Individuals who were pregnant or underweight were excluded.
How the study was conducted
Body mass index (BMI) was classified into three categories: normal weight, overweight, and obesity, according to standard clinical definitions. Investigators identified obesity-related conditions using consensus definitions and the data available from NHANES. Conditions examined included:
- Prediabetes and type 2 diabetes
- Hypertension
- Dyslipidaemia
- Asthma
- Stress urinary incontinence
- Liver steatosis
- Kidney hyperfiltration
- Probable obstructive sleep apnoea
Relative risks for each condition were calculated by comparing individuals with obesity or overweight to those with normal BMI, while adjusting for factors such as age, sex, insurance status, access to health care, and survey cycle. The researchers then estimated population attributable fractions (PAFs), which indicate the proportion of each condition that could be attributed to overweight or obesity.
Study findings
Among adolescents, 18.7% had overweight and 22.3% had obesity. Among young adults, 25.8% had overweight and 29.7% had obesity. Prevalence of obesity-related conditions varied widely — from 0.3% for type 2 diabetes in adolescents to 36.4% for liver steatosis in young adults.
The analysis showed that obesity made a striking contribution to the overall disease burden:
- Adolescents – Six of seven measured conditions showed significant PAFs due to obesity, ranging from 10.2% for asthma to 49.6% for liver steatosis.
- Young adults – Eight of nine conditions showed significant obesity-attributable fractions, ranging from 10.4% for asthma to 78.9% for type 2 diabetes.
Overweight status also contributed to disease burden, though to a lesser extent. For adolescents, PAFs due to overweight ranged from 6.2% for asthma to 13.1% for liver steatosis. In young adults, overweight contributed to 10.0% of hypertension cases and 21.0% of liver steatosis cases.
The study authors concluded: “Large portions of ORCs in US adolescents and young adults may be attributable to obesity and, to a lesser extent, overweight.”
Implications for prevention and treatment
The findings underscore the critical role of obesity in the early development of chronic disease. The researchers highlighted that obesity-related conditions arising in adolescence or young adulthood increase the risk of more severe disease later in life.
They noted: “These PAFs can inform estimates of the potential impact of expanding access to behavioural, surgical, and pharmacotherapeutic interventions, including glucagon-like peptide-1 receptor agonists, on reducing ORCs in US youth.”
Limitations
The study acknowledged several limitations. Its cross-sectional design assumed causality between obesity and obesity-related conditions, which cannot be proven definitively. Reliance on self-reported data introduced the risk of recall bias, and there was a possibility of misclassifying diabetes subtypes. The researchers also noted the potential for confounding factors, such as independent precursors that may contribute to both obesity and associated conditions.
Conclusion
Obesity remains a major driver of chronic disease among adolescents and young adults in the United States. While overweight status contributes to some extent, obesity accounts for much larger proportions of conditions such as liver steatosis, hypertension, and type 2 diabetes.
The authors emphasised that intervening early in life — through prevention and treatment strategies — may reduce both the long-term health impact and the associated economic burden of these conditions.
CCH Insight:
The findings of this study are, in a way, quite shocking – the fact that large numbers of young people have liver disease, prediabetes and hypertension, conditions that were once associated with the later stages of life. However, the rising prevalence of child and adolescent obesity over recent decades means this has been sadly predictable, and it is a ticking time-bomb in terms of chronic diseases, disability, premature mortality and health and social care costs. As the authors stated, it is vital that obesity is addressed from the earliest opportunity, including access to GLP-1 medications.
Read More
Childhood obesity associated with structural changes in foot shape
Key Takeaways:
- A large international study published in BMC Pediatrics has identified a significant link between childhood obesity and changes in foot morphology.
- Using advanced photogrammetry techniques, researchers found that children with higher BMI were more likely to present wider and flatter feet, with potential consequences for mobility and musculoskeletal health.
- The findings highlight the importance of considering foot structure in obesity management and suggest the need for tailored footwear, early interventions, and holistic public health strategies.
Rising childhood obesity and its overlooked consequences
Childhood obesity continues to rise at concerning rates worldwide, prompting extensive research into its impact on health and development. While much of the scientific focus has traditionally been on metabolic or cardiovascular complications, a new international study has turned attention towards a less-examined area – foot morphology. The research provides new insights into how excess body weight may affect the structure of children’s feet and the implications this has for mobility and long-term musculoskeletal health.
Understanding foot morphology
Foot morphology refers to the anatomical shape and structure of the foot, including features such as arch height, width, and length. In children, whose bones and musculoskeletal systems are still developing, these structures are particularly sensitive to external pressures such as excess weight. While previous studies have linked obesity to chronic conditions such as diabetes or hypertension, few have explored how it alters the structural integrity of the body during growth.
The team of researchers – Hakan Büyükçelebi, Mahmut Açak, Özgür Eken, Adem Doğaner, Gökmen Özen, and Luca Paolo Ardigò – set out to address this gap by analysing how obesity correlates with variations in foot structure.
Advanced use of photogrammetry
To capture precise data, the researchers used state-of-the-art photogrammetry. This imaging technique builds detailed three-dimensional models from photographs, allowing highly accurate measurement of anatomical features. Unlike traditional measuring methods, photogrammetry is non-invasive and child-friendly, reducing discomfort during assessment.
Each participant’s foot was digitally scanned, producing accurate records of structural features such as arch height, foot length, and width. These digital models enabled the team to identify subtle but consistent differences in foot shape across groups of children categorised by Body Mass Index (BMI).
Large and diverse study sample
The cross-sectional study engaged children from a wide range of backgrounds and geographical locations, improving the reliability and generalisability of the results. Participants were grouped according to BMI, and their foot morphology was carefully compared.
The data revealed clear patterns. Children with higher BMI tended to have feet that were wider and flatter than those of children in a healthy weight range. Conversely, children with BMI within standard limits displayed foot shapes more typically associated with healthy biomechanics.
Findings and implications for children’s health
The study suggests that children living with obesity may be more susceptible to structural changes in the foot that affect overall mobility. “Wider and flatter foot shapes were prevalent among obese children,” the researchers noted, raising concerns about increased risk of pain, discomfort, and potential musculoskeletal injuries.
These structural changes can alter gait and movement patterns, potentially leading to joint strain or other biomechanical problems as children grow. The implications extend beyond immediate discomfort. Altered foot morphology may increase vulnerability to long-term mobility limitations, impacting physical activity and overall health.
The role of footwear and early interventions
One practical consideration arising from the study is footwear. Children with altered foot morphology may require specially designed shoes that provide adequate support and prevent further complications. Standard footwear may not meet the needs of children with wider, flatter feet, potentially exacerbating problems.
The researchers highlight the importance of recognising these needs early and encouraging parents, educators, and healthcare professionals to consider foot health as part of obesity management. Promoting healthy weight, encouraging physical activity, and ensuring supportive footwear could together help safeguard mobility and comfort in growing children.
Broader public health significance
The findings also reinforce the urgent need for comprehensive strategies to address childhood obesity. As the researchers note, excess weight has “multifaceted consequences,” with foot morphology being one aspect of a much wider issue. The study underscores that obesity does not only affect internal systems but also the very structures that underpin daily movement.
Public health initiatives that encourage balanced nutrition, regular activity, and healthy environments for children may reduce not only metabolic risks but also structural complications such as those observed in foot shape.
Future directions for research
The study paves the way for future investigations into related areas. Longitudinal studies could help determine how these morphological changes evolve over time and whether early interventions can reverse or mitigate their effects. Researchers may also examine whether obesity influences other structural aspects of the musculoskeletal system, such as the spine or lower limb joints.
Additionally, there is scope for exploring the effectiveness of footwear specifically designed for children with altered foot structures, assessing whether targeted design can improve mobility outcomes and reduce injury risk.
Conclusion
This large-scale study provides compelling evidence of a link between childhood obesity and changes in foot morphology. The use of advanced photogrammetry offered detailed insights into how excess weight may alter the developing foot, with potential implications for gait, mobility, and injury risk.
By drawing attention to foot structure, the research underscores the importance of addressing childhood obesity in a holistic manner. As Hakan Büyükçelebi and colleagues highlight, the medical community should consider foot health as an integral part of assessment and management.
In doing so, society can take one step closer to ensuring that children receive comprehensive support for healthier, more active futures.
Read More
Study highlights ways to improve primary care visits for people living with obesity
Key Takeaways:
- A new study led by Drexel University shows that people living with obesity strongly prefer primary care visits that emphasise empathy, respect, and freedom from stigma.
- Surveyed participants rated an “ideal” visit scenario at 9.4 out of 10, citing the importance of attentive listening, respectful communication, and not attributing all health concerns solely to weight.
- Researchers recommend that clinician training, office practices, and referral systems should explicitly address weight stigma, with a greater focus on patient-centred, respectful care.
Understanding barriers in primary care
Accessing health care can be difficult under any circumstances, but systemic barriers make the experience particularly challenging for some groups. For people living with obesity, weight-related stigma and inequities in health care often negatively influence their experiences when visiting primary care physicians. Such encounters can lead to frustration, mistrust, and in some cases, avoidance of care altogether.
Redesigning the “ideal” primary care visit
To address these challenges, researchers at Drexel University’s College of Nursing and Health Professions worked with people living with obesity to explore what an “ideal” primary care visit might look like. Their findings, recently published in Patient Education and Counseling, provide an evidence-based model for improving everyday interactions between clinicians and patients.
The project was conducted in two phases.
In the first phase, the Obesity Action Coalition (OAC) partnered with Thoughtform, an experience design studio, to work directly with people who have obesity. Participants shared their personal experiences, highlighting both barriers and possible solutions within primary care. Concerns included a limited sense of rapport with clinicians and the lack of appropriate physical resources such as larger blood pressure cuffs or gowns that fit comfortably.
From these discussions, OAC and Thoughtform developed a story-based narrative that illustrated a more positive primary care experience. The scenario depicted a setting where patients were listened to, treated kindly, and not judged for their weight. Illustrations were included to help visualise these improvements.
Validating the “ideal” model with patient input
In the second phase, the research team surveyed 250 American adults living with obesity, asking them to compare the “ideal” scenario with their most recent real-life doctor’s visit. The results were clear: participants overwhelmingly preferred the redesigned model, giving it an average rating of 9.4 out of 10.
Respondents highlighted several aspects that made the “ideal” scenario preferable. These included clinicians who:
- listened attentively,
- showed respect,
- avoided attributing every health issue to weight, and
- referred patients to specialists who treated them with empathy and professionalism.
“The survey results showed that people living with obesity want empathetic, respectful health care,” explained Kristal Lyn Brown, PhD, assistant professor in the College and lead author of the study. “We hope these results encourage providers and their staff to make their spaces more inclusive and free of weight bias and stigma.”
The value of empathy and common sense in care
Brown emphasised that the findings underscore the importance of recognising patients’ humanity.
“People with obesity are asking for basic, every day, human interactions — not resource-intensive changes but literally common-sense practices, of which our primary care offices often fall short,” she said.
The study suggests that simple changes in tone, communication, and approach can make a significant difference. By fostering empathy and respect, health care teams may help patients feel more comfortable attending primary care appointments, reducing the risk of avoidance. Over time, these practices could also build greater trust between providers and patients.
Recommendations for practice and training
Based on the findings, the research team outlined several key recommendations:
- Clinician training should explicitly address weight stigma and promote patient-centred, respectful communication.
- Front office staff should be trained to recognise and address bias, as the patient experience often begins at reception.
- Referral practices should prioritise specialists known for respectful and empathetic care.
- Patient-centred dialogue should allow individuals to tell their story without assumptions that every concern is weight-related.
Including patient voices in systemic change
Brown stressed that beyond individual practice, the study highlights the value of including patient voices in the design of health systems and research projects. Actively partnering with people living with obesity ensures that proposed solutions address real-world needs, and helps create care environments that are inclusive, respectful, and free from stigma.
Read More